Eyelid eversion is a simple maneuver that exposes the upper tarsal conjunctiva for direct inspection.
The upper tarsus hides many diagnoses, from retained foreign bodies to trachomatous scarring.
However, many examiners skip it in a busy clinic.
Why the Upper Tarsus Matters
The superior palpebral conjunctiva rubs against the cornea with every blink.
Therefore, a particle trapped there scratches the epithelium repeatedly.
In addition, chronic allergic and infectious diseases show their typical signs on this surface.
Without eversion, these findings stay invisible at the slit lamp.
Indications for Eyelid Eversion
- Foreign body sensation with a clear cornea or vertical linear abrasions
- Chronic red eye without an obvious cause
- Suspected trachoma, allergic or contact lens related conjunctivitis
- Chemical injury, to find retained particles
- Unexplained mucous discharge or lid swelling
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteWhen to Avoid Eyelid Eversion
Never evert the lid when you suspect an open globe.
Pressure on the lid can then extrude intraocular contents.
Also, defer the maneuver after recent intraocular or lid surgery unless the benefit is clear.
In these cases, a careful external exam and imaging come first (see intraocular foreign body).
Preparing the Patient
First, explain that the lid will turn over and that the sensation is odd but brief.
Next, instill a topical anesthetic if the eye is painful or blepharospasm is present.
Then, position the patient at the slit lamp with chin and forehead firmly in place (see slit lamp exam).
Single Eyelid Eversion Technique
- Ask the patient to look down and keep looking down.
- Grasp the central upper lashes gently between thumb and index finger.
- Place a cotton-tipped applicator at the upper border of the tarsus, near the lid crease.
- Pull the lashes down and slightly away from the globe.
- Then lift the lashes upward while pressing the applicator gently downward.
- Remove the applicator and hold the lashes against the brow with your thumb.
Double Eyelid Eversion
Single eversion exposes the tarsus but leaves the superior fornix hidden.
In double eversion, the examiner places a Desmarres retractor on the skin above the everted tarsus and rolls it outward.
As a result, the upper fornix comes into direct view.
This step is essential after chemical injury, because lime or plaster particles can hide deep in the fornix.
A moistened swab can then sweep the fornix under topical anesthesia.
Examining the Lower Lid
The lower lid needs no formal eversion.
Simply ask the patient to look up while you pull the lower lid down with a finger.
Then inspect the inferior tarsal conjunctiva and fornix.
What to Look for After Eyelid Eversion
Scan the tarsus systematically under diffuse light, then with a narrow slit beam.
Also, fluorescein with cobalt blue light highlights papillae and tiny particles.
Check the sulcus subtarsalis, a shallow groove about 2 mm from the lid margin.
Small foreign bodies often lodge in this groove and cause vertical corneal abrasions (see corneal foreign body).
Papillae on Eyelid Eversion
Papillae appear as raised polygonal bumps with a central vascular core.
Fine papillae accompany many nonspecific irritations.
However, giant papillae larger than 1 mm suggest giant papillary conjunctivitis or vernal keratoconjunctivitis.
Therefore, evert the lid in contact lens wearers who report mucus or lens intolerance.
Follicles and Trachoma
Follicles look like pale, avascular, rounded elevations with vessels at their edge.
The WHO simplified grading system defines follicular trachoma (TF) by follicles on the central upper tarsus.
It requires five or more follicles, each at least 0.5 mm in diameter.
Therefore, eversion is mandatory in every trachoma survey.
Arlt’s Line on Eyelid Eversion
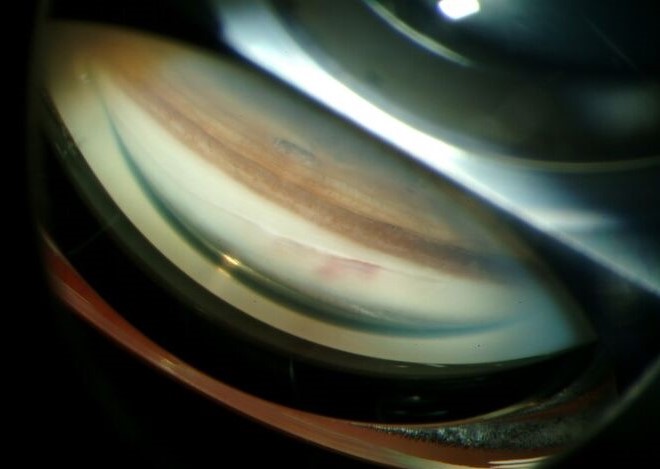
Arlt’s line is a horizontal white scar band across the upper tarsal conjunctiva.
It reflects trachomatous scarring (TS) after repeated infection.
Next, examine the lid margin for trichiasis and entropion.
Also, other cicatrizing diseases can scar the tarsus, so correlate with the history.
Other Tarsal Findings
- Concretions, yellow-white deposits that can erode and scratch the cornea
- Membranes or pseudomembranes in severe adenoviral conjunctivitis
- The conjunctival face of a chalazion or pyogenic granuloma
- A lax, rubbery tarsus that everts too easily, as in floppy eyelid syndrome
- A lost contact lens or lens fragment
Returning the Lid
Ask the patient to look up while you gently pull the lashes forward.
The lid then rolls back into its normal position.
Finally, recheck the cornea for fresh staining from the exam.
Pitfalls to Avoid
- Letting the patient look up during eversion, which makes the lid spring back
- Pressing on the globe with the applicator
- Stopping at single eversion after a chemical injury
- Missing the sulcus subtarsalis, where particles hide
- Labeling every tarsal scar as trachoma
For the latest studies, see the PubMed results for eyelid eversion.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Bowling B. Kanski’s Clinical Ophthalmology: A Systematic Approach. 8th ed. Edinburgh: Elsevier; 2016.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 8: External Disease and Cornea. San Francisco: AAO; 2023.
- Thylefors B, Dawson CR, Jones BR, West SK, Taylor HR. A simple system for the assessment of trachoma and its complications. Bull World Health Organ. 1987;65:477-483.
- Solomon AW, Kello AB, Bangert M, et al. The simplified trachoma grading system, amended. Bull World Health Organ. 2020;98:698-705.
- Allansmith MR, Korb DR, Greiner JV, et al. Giant papillary conjunctivitis in contact lens wearers. Am J Ophthalmol. 1977;83:697-708.
Test yourself
A few questions straight from this article.
-
In which situation must upper eyelid eversion never be performed?
Never evert the lid when an open globe is suspected, because pressure on the lid can extrude intraocular contents; external exam and imaging come first. -
Where should the patient look during single eyelid eversion?
The patient looks down and keeps looking down, because looking up during eversion makes the lid spring back. -
Where is the cotton-tipped applicator placed for single eyelid eversion?
The applicator sits at the upper tarsal border near the lid crease; the lashes are pulled down and away, then lifted while the applicator presses gently downward. -
Why is double eyelid eversion essential after a chemical injury?
Single eversion leaves the superior fornix hidden; a Desmarres retractor brings it into view, which matters because lime or plaster particles can hide deep there. -
Where is the sulcus subtarsalis, a site seen after eyelid eversion?
The sulcus subtarsalis is a shallow groove about 2 mm from the lid margin where small foreign bodies often lodge and cause vertical corneal abrasions. -
On the everted upper tarsus, which finding separates papillae from follicles?
Papillae are raised polygonal bumps with a central vascular core, while follicles are pale, avascular, rounded elevations with vessels at their edge. -
On eyelid eversion, what size makes papillae giant and suggests giant papillary conjunctivitis or vernal keratoconjunctivitis?
Fine papillae accompany many nonspecific irritations, but giant papillae larger than 1 mm suggest giant papillary conjunctivitis or vernal keratoconjunctivitis. -
Which finding on the central upper tarsus defines follicular trachoma (TF) in the WHO simplified grading system?
TF requires five or more follicles, each at least 0.5 mm in diameter, on the central upper tarsus, so eversion is mandatory in every trachoma survey. -
What does Arlt's line on the everted upper tarsus represent?
Arlt's line is a horizontal white scar band across the upper tarsal conjunctiva reflecting trachomatous scarring (TS) after repeated infection. -
How is the upper lid returned to its normal position after eversion?
Ask the patient to look up while gently pulling the lashes forward; the lid rolls back, and the cornea is then rechecked for fresh staining.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.