
Corneal collagen cross-linking (CXL) uses riboflavin and ultraviolet-A light to increase covalent bonding between corneal collagen fibrils, mechanically stiffening the cornea. It is the standard of care for documented progressive keratoconus, and its main effect is to stop the disease from getting worse rather than to improve vision.
That distinction is worth stating plainly to patients before they consent to the procedure, since some arrive expecting a refractive treatment.
Beyond keratoconus, cross-linking is used for post-refractive ectasia following LASIK or PRK performed on a cornea that was unrecognised as thin or borderline at the time, and for pellucid marginal degeneration with documented progression. It also has an adjunctive antimicrobial role in certain infectious keratitis, which is a separate application from its use in ectatic disease and works through a different mechanism.
Mechanism
Riboflavin is applied to the corneal surface as a photosensitiser, either after epithelial removal or, in some protocols, through an intact epithelium. Ultraviolet-A light at a specific wavelength and irradiance activates the riboflavin, generating reactive oxygen species that induce new covalent bonds within and between collagen fibrils in the stroma.
The resulting increase in biomechanical stiffness is what halts progressive steepening.
Treatment effect is concentrated in the anterior stroma, which is both the region of greatest biomechanical significance and the reason minimum corneal thickness requirements exist: adequate stroma above the endothelium protects it from UV-related damage during treatment.
Cross-linking does not reshape or flatten the cornea in a way that reliably improves vision. Some patients do see modest visual improvement afterward, but this is a secondary and inconsistent effect, not the goal of the procedure.
Patient Selection
The key requirement is documented progression, not simply a diagnosis of keratoconus. This is usually defined as a significant increase in maximum keratometry, a defined change in manifest refraction, or measurable thinning over a defined follow-up interval.
A stable cornea gives the procedure nothing to stop, so treating on the diagnosis alone, without evidence of change over time, is a common and avoidable error.
Corneal thickness needs to be adequate, conventionally at least 400 microns at the thinnest point after epithelial removal, to keep the endothelium safe from UV exposure. Active infection, significant scarring that would limit any benefit, and a history of poor epithelial healing are relative contraindications.
Younger patients are treated preferentially where possible, since disease progression is typically most active in the second and third decades of life, and catching it early gives the best chance of preserving useful vision without needing a corneal transplant later.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteProcedure
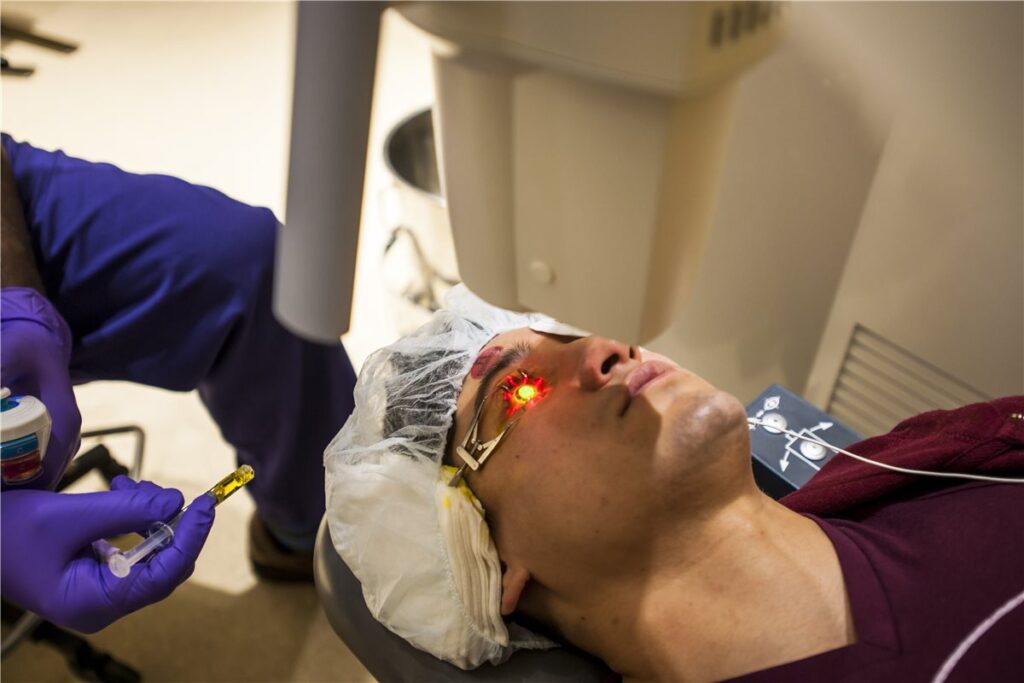
In the standard, or epithelium-off, protocol, the central corneal epithelium is removed to allow riboflavin to penetrate the stroma adequately. Riboflavin drops are instilled over a soak period, with slit-lamp confirmation of stromal saturation before UV exposure begins, and the UV-A light is then applied for a defined exposure time with riboflavin instillation continuing throughout.
This remains the most extensively validated protocol and has the longest track record of outcome data.
Epithelium-on, or transepithelial, protocols leave the epithelium intact and rely on enhanced riboflavin formulations or adjunctive techniques to improve penetration. The appeal is faster visual recovery, less postoperative pain, and lower infection risk.
Current evidence suggests this comes at some cost in efficacy compared with the epithelium-off approach, and most cornea specialists do not yet regard the two as equivalent for halting progression.
A bandage contact lens is typically placed after epithelium-off treatment to reduce pain and support epithelial healing, along with topical antibiotics and corticosteroids during recovery. Follow-up imaging over the following year confirms that the topographic and biomechanical parameters being tracked have stabilised.
Outcomes and Evidence
Randomised controlled trials have consistently shown that cross-linking halts or slows progression in the large majority of treated eyes, compared with continued progression in untreated controls.
A modest flattening effect with small gains in uncorrected and best-corrected visual acuity is seen in many patients, though this remains a secondary benefit rather than the primary treatment goal.
Follow-up data now extending beyond a decade continue to show durable stabilisation in most treated eyes, and in regions where cross-linking programmes have been established for some years, population-level data show a measurable reduction in the rate of corneal transplantation performed for keratoconus.
That reduction in transplant rates, seen at a population level rather than just within trial cohorts, is probably the most convincing evidence of the procedure’s real-world value.
Complications
- Delayed epithelial healing and postoperative pain, generally self-limiting with the epithelium-off technique
- Infectious keratitis, uncommon but reported, and requiring prompt recognition given the compromised epithelial barrier during healing
- Sterile corneal infiltrates, a self-limited inflammatory reaction distinct from true infection
- Corneal haze, usually transient, though persistent haze occasionally affects visual outcome
- Endothelial cell loss, rare when the minimum thickness criteria are respected
- Treatment failure with continued progression despite cross-linking, occurring in a minority of eyes and sometimes prompting a repeat procedure
Most serious complications on this list trace back to either inadequate corneal thickness at the time of treatment or a lapse in epithelial and infection precautions during healing, both of which are largely avoidable with careful patient selection and postoperative care.
Prognosis
The majority of appropriately selected patients achieve durable stabilisation of their keratoconus. Vision is generally preserved at or near its pre-treatment level, with a meaningful minority experiencing some improvement.
Patients treated later in the disease course, after significant ectasia and scarring have already set in, gain less from cross-linking and may still need a corneal transplant despite treatment.
Ongoing topographic monitoring remains appropriate even after apparently successful treatment, since disease can occasionally continue to progress.
In practical terms, cross-linking has turned progressive keratoconus, once a disease that reliably worsened over years, into one that mostly does not, provided it is caught early enough. It cannot undo damage the disease has already caused before treatment.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Wollensak G, Spoerl E, Seiler T. Riboflavin/ultraviolet-A-induced collagen crosslinking for the treatment of keratoconus. American Journal of Ophthalmology. 2003.
- Hersh PS, Stulting RD, Muller D, et al. United States multicenter clinical trial of corneal collagen crosslinking for keratoconus treatment. Ophthalmology. 2017.
- Sykakis E, Karim R, Evans JR, et al. Corneal collagen cross-linking for treating keratoconus. Cochrane Database of Systematic Reviews. 2015.
- Corneal Collagen Cross-Linking. EyeWiki, American Academy of Ophthalmology.
- Keratoconus and Corneal Cross-Linking. StatPearls, NCBI Bookshelf.
Test yourself
A few questions straight from this article.
-
What is the primary treatment goal of corneal collagen cross-linking in progressive keratoconus?
Cross-linking stabilises the cornea rather than restoring vision. Modest visual improvement occurs in some patients, but it is a secondary and inconsistent effect that should not be promised at consent. -
By what mechanism does corneal cross-linking stiffen the cornea in keratoconus?
Riboflavin acts as a photosensitiser; UV-A activation generates reactive oxygen species that induce new covalent bonds within and between stromal collagen fibrils. The resulting biomechanical stiffening halts progressive steepening. -
Which requirement must be met before offering cross-linking for keratoconus?
The key requirement is documented change, usually a significant rise in maximum keratometry, a defined refractive shift, or measurable thinning. A stable cornea gives the procedure nothing to stop. -
What minimum corneal thickness at the thinnest point is conventionally required after epithelial removal for cross-linking?
At least 400 microns of stroma is conventionally required after the epithelium is removed. Adequate stroma above the endothelium shields it from ultraviolet-related damage during treatment. -
Besides keratoconus, which condition is a recognised indication for corneal cross-linking?
Cross-linking is used for ectasia developing after LASIK or PRK on a cornea that was thin or borderline but unrecognised at the time. Pellucid marginal degeneration with documented progression is another accepted indication. -
Which cross-linking protocol is the most extensively validated with the longest outcome data?
Removing the central epithelium allows adequate riboflavin penetration and remains the best-validated approach. Epithelium-on protocols offer faster recovery and less pain, but current evidence suggests some loss of efficacy. -
Why are younger patients with keratoconus treated preferentially with cross-linking?
Keratoconus progresses most actively in the second and third decades of life. Treating early gives the best chance of preserving useful vision and avoiding a corneal transplant later. -
Which complication after cross-linking is a self-limited inflammatory reaction rather than true infection?
Sterile infiltrates are an inflammatory reaction distinct from true infectious keratitis. Distinguishing the two matters, since the epithelial barrier is compromised during healing and genuine infection needs prompt recognition. -
Which population-level finding is the most convincing evidence of cross-linking's real-world value in keratoconus?
Where cross-linking programmes have run for some years, population data show a measurable reduction in corneal transplantation performed for keratoconus. This real-world signal is stronger evidence than trial cohort outcomes alone. -
What outcome should be expected when cross-linking is performed late, after significant ectasia and scarring?
Patients treated after substantial ectasia and scarring gain less from cross-linking and may still require a corneal transplant. The procedure cannot undo damage the disease has already caused.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.


