CASE REPORT
A 39-years-old man presented to a clinic with complaints of decreased blurred vision and floaters in his left eye over the previous two weeks.
His best-corrected visual acuity at the initial presentation was 20/ 20 in the right eye and hand movement in the left eye. The anterior segment and intraocular pressure were normal.
The visual field using the Goldmann perimeter and the Humphrey static achromatic automatic perimetry (central 30-2 threshold test) was normally at the right eye and could not be performed on the left eye owing to the markedly decreased visual acuity.
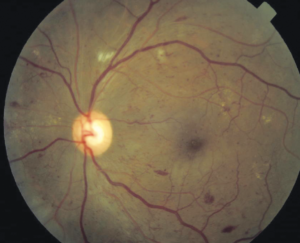
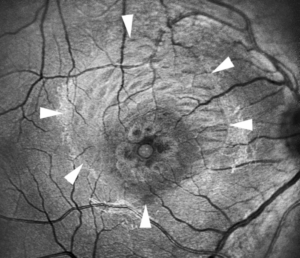
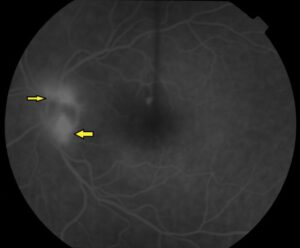
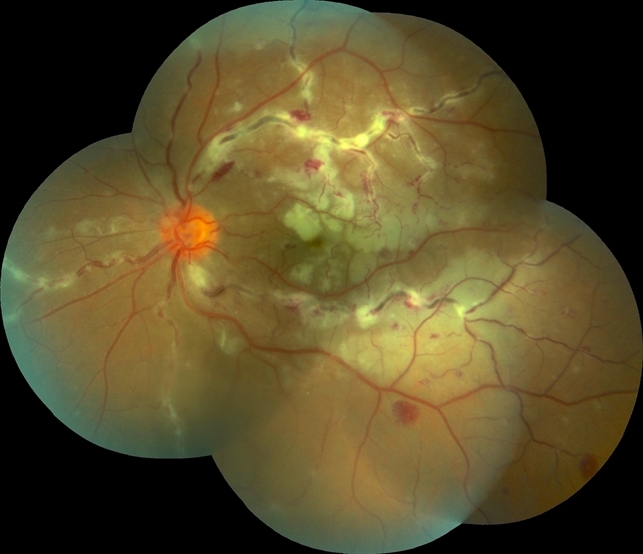
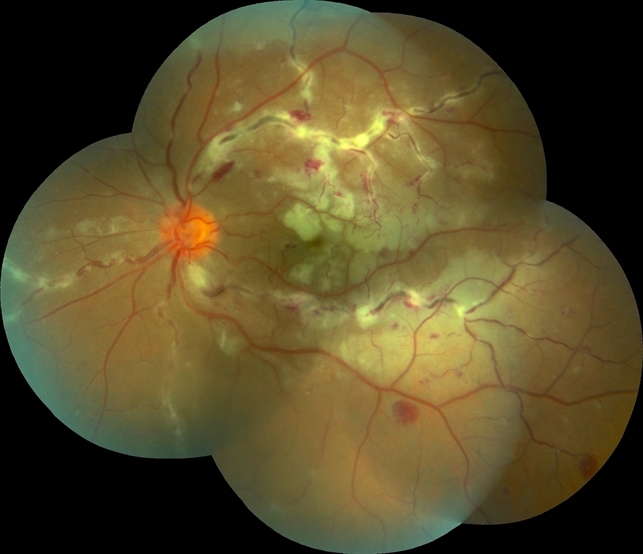
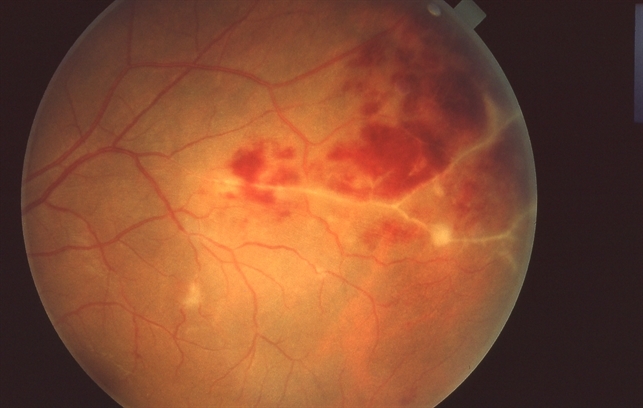
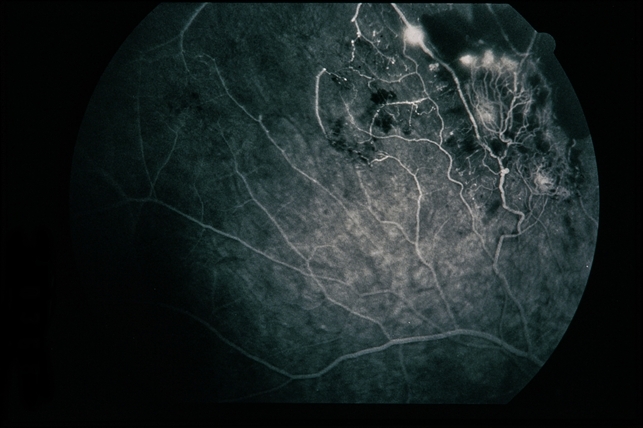
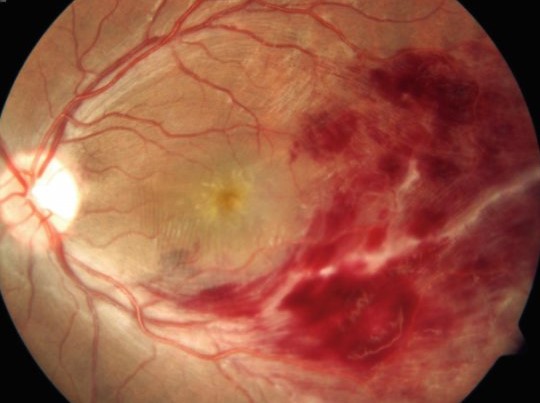
Ultrasonography of the left eye highlighted dense vitreous floaters, which obscured the view of the fundus. Dilated ocular fundus examination of the right eye showed pallor of the optic nerve head; temporally from the macula in the mid-periphery, there were perivascular sheathing, scattered wet perivascular exudates, dotted and flame-shaped intraretinal hemorrhages, focal occlusions of retinal vessels, extensive nonperfused areas of the capillaries from the macula in the mid-retina periphery, which extended towards the posterior pole and retinal periphery, giving rise to preretinal neovascularization prominent into the vitreous in the fashion of a sea fan.
Taking into account all the clinical, angiographic, and ultrasonographic assessments, the diagnoses of bilateral Eales disease in the late (proliferative) stage with neovascularization and retinal and vitreous hemorrhages were established.
DISEASE
Eales’ disease was first described by British ophthalmologist Henry Eales in 1880. Eales’ disease is an idiopathic occlusive vasculitis involving the mid-peripheral retina that is characterized by retinal venous inflammation (periphlebitis), vascular occlusion, and subsequent retinal neovascularization.
A hallmark of Eales’ disease is recurrent vitreous hemorrhage.
Eales’ disease mainly affects young males, with a mean age at presentation of around 30 years. It is more prevalent in India and Middle Eastern countries with cases observed worldwide.
In a study by Biswas et al., a male-to-female ratio of 20:1 was observed with a mean age at presentation of 29.9 years, with a range from 11– 59 years.
It remains a diagnosis of exclusion, made only after a careful search for the many recognized causes of retinal vasculitis and peripheral vascular occlusion has failed to identify a specific underlying etiology, despite decades of study into a possible infectious or immunologic trigger.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteClinical Course
The disease classically progresses through overlapping stages: an initial phase of peripheral retinal vasculitis, most often periphlebitis, followed by peripheral vascular non-perfusion, and eventually neovascularization arising from the areas of ischemia.
Once neovascular vessels form, they are fragile and prone to bleeding into the vitreous, which is what produces the recurrent vitreous hemorrhage that is often the presenting complaint bringing a young, previously asymptomatic patient to medical attention.
The disease is frequently bilateral, though the two eyes can be affected asymmetrically and at different points in their individual disease course, meaning one eye may be actively hemorrhaging while the other shows only early, asymptomatic peripheral vasculitis.
Clinical Presentation
- Sudden painless vision loss or floaters from vitreous hemorrhage, often the presenting complaint in a young, healthy adult male with no prior ocular history
- Peripheral retinal vascular sheathing and inflammation on exam of the fellow or less severely affected eye, when the view allows adequate visualization
- Peripheral neovascularization, best appreciated on fluorescein angiography, arising at the border of perfused and non-perfused peripheral retina
- A demographic pattern strongly skewed toward young adult men, typically in their twenties or thirties, a distinctive epidemiologic clue that helps distinguish Eales disease from many of its mimics
Differential Diagnosis
Diabetic retinopathy can produce a broadly similar picture of peripheral non-perfusion and neovascularization, but typically occurs in an older patient with an established diabetes history and a different, more central pattern of vascular change.
Retinal vein occlusion, sickle cell retinopathy, and sarcoidosis-associated retinal vasculitis, discussed in relation to ocular sarcoidosis in its own dedicated article on this site, all need to be actively excluded given their overlapping potential to produce peripheral vasculitis and non-perfusion.
Infectious causes, particularly tuberculosis, have long been proposed as a possible trigger for Eales disease specifically, and a history and workup for latent or active tuberculosis exposure is a standard part of the evaluation in endemic regions, even though the exact causal relationship remains unproven.
Diagnostic Evaluation
Fluorescein angiography is essential for mapping the extent of peripheral non-perfusion and identifying areas of active or subclinical neovascularization, guiding both diagnosis and subsequent laser treatment planning.
A thorough systemic workup, including screening for diabetes, sickle cell disease, sarcoidosis, tuberculosis, and other systemic vasculitides, is necessary to support the diagnosis of exclusion, since Eales disease cannot be confidently diagnosed until these other causes have been reasonably ruled out.
B-scan ultrasonography, discussed in its own dedicated article on this site, is useful when vitreous hemorrhage precludes an adequate direct view of the retina, helping assess for an underlying retinal detachment that would change the urgency and approach to treatment.
MANAGEMENT
General Treatment
The management of Eales’ disease depends upon the stage of the disease. The treatment strategy consists of medical treatment with oral corticosteroids in the active inflammatory stage and laser photocoagulation for retinal ischemia and neovascularization.
Biswas et al. observed that the timely use of oral corticosteroid during active inflammation and the use of laser ablation of areas with capillary non-perfusion had a statistically significant beneficial impact on visual outcomes during a 10-year follow-up period.
Peripheral scatter laser photocoagulation is applied to areas of retinal non-perfusion and neovascularization, following the same general treatment logic used for other ischemic retinal diseases, aiming to reduce the angiogenic drive behind ongoing neovascularization and hemorrhage risk.
Corticosteroids or other immunosuppressive therapy may be used during the active vasculitic phase to control inflammation, particularly when active periphlebitis is present alongside the ischemic and neovascular findings.
Vitrectomy is reserved for eyes with non-clearing vitreous hemorrhage, tractional retinal detachment, or other complications that do not resolve with laser and medical management alone, following similar surgical principles to other proliferative retinal vascular diseases.
Because both eyes are frequently involved even when only one is currently symptomatic, careful examination and monitoring of the fellow eye is a standard, essential part of managing every confirmed case.
Medical Treatment
- Corticosteroids
- Anti-Vascular Endothelial Growth Factor (Anti-VEGF)
- Anti-Tuberculosis Treatment
- Photocoagulation
- Surgical treatment


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteREFERENCES
- Eales H. Primary retinal hemorrhage in young men. Ophthalmic Rev. 1882;1: 41.
- Biswas J, Ravi RK, Naryanasamy A, Kulandai LT, Madhavan HN. Eales’ disease – current concepts in diagnosis and management. J Ophthalmic Inflamm Infect. 2013;3(1):11.
- Das T, Pathengay A, Hussain N, Biswas J. Eales’ disease: diagnosis and management. Eye (Lond). 2010;24(3):472-82.
- Biswas J, K R R, Pal B, Gondhale HP, Kharel Sitaula R. Long-Term Outcomes of a Large Cohort of Patients with Eales’ Disease. Ocul Immunol Inflamm. 2018;26(6):870‐876.
- Ishaq M, Karamat S, Niazi MK. HLA typing in patients of Eales disease. J Coll Physicians Surg Pak. 2005 May; 15(5):288-90.
- Rajesh M, Sulochana KN, Coral K, et al. Determination of carbonyl group content in plasma proteins as a useful marker to assess impairment in antioxidant defense in patients with Eales’ disease. Indian J Ophthalmol. 2004;52(2):139-144.
- Biswas J, Sharma T, Gopal L, et al. Eales disease: an update. Survey of Ophthalmology.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 12: Retina and Vitreous.
- Saxena S, Kumar D. Eales disease: an update. Journal of Postgraduate Medicine.
Test yourself
A few questions straight from this article.
-
How is Eales' disease best defined?
Eales' disease is an idiopathic occlusive vasculitis of the mid-peripheral retina, marked by retinal venous inflammation, vascular occlusion and later neovascularization. -
What is regarded as the hallmark of Eales' disease?
Recurrent vitreous hemorrhage is described as the hallmark of Eales' disease, following the periphlebitis and vascular occlusion that define it. -
What male-to-female ratio was observed in the Biswas study of Eales' disease?
Biswas and colleagues observed a male-to-female ratio of 20 to 1 in their cohort of patients with Eales' disease. -
In which regions is Eales' disease reported to be more prevalent?
Although cases are seen worldwide, Eales' disease is more prevalent in India and in Middle Eastern countries. -
Which fundus appearance describes the preretinal neovascularization of proliferative Eales' disease?
In the proliferative stage the preretinal new vessels project prominently into the vitreous in the fashion of a sea fan, arising from extensive non-perfused retina. -
What primarily guides the choice of treatment in Eales' disease?
Management of Eales' disease depends upon the stage, with anti-inflammatory treatment for active disease and laser for ischemia and neovascularization. -
Which treatment is used during the active inflammatory stage of Eales' disease?
Medical treatment in the active inflammatory stage rests on oral corticosteroids, with laser reserved for retinal ischemia and neovascularization. -
How did the reported patient with Eales' disease first present?
The 39-year-old man presented with decreased blurred vision and floaters in the left eye over the preceding two weeks, with hand movement acuity on that side. -
Which systemic therapy is listed among the medical treatments for Eales' disease?
The medical treatment options listed for Eales' disease include corticosteroids, anti-VEGF agents and anti-tuberculosis treatment, alongside photocoagulation and surgery. -
Over a 10-year follow-up, which approach significantly improved visual outcomes in Eales' disease?
Biswas and colleagues found that timely oral corticosteroid during active inflammation, combined with laser ablation of areas of capillary non-perfusion, had a statistically significant benefit on vision.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.