Chronic retinal detachment is a rhegmatogenous detachment that has been present for weeks to months before diagnosis.
It usually develops slowly, and many patients notice little until central vision falls. However, the fundus keeps a record of time, so reading that record helps the surgeon plan a safer repair.
Who Develops Chronic Retinal Detachment
Young myopic patients with atrophic holes in lattice degeneration form a typical group, and a retinal dialysis after blunt trauma often causes a slow inferotemporal detachment. In these eyes the vitreous is usually attached, so fluid spreads slowly, and as a result the detachment can creep for months without alarming symptoms.
Symptoms That Hide Chronicity
Patients rarely report a shower of floaters or flashes, and instead they describe a vague shadow, or the problem appears at a routine exam. Some notice reduced vision only when the macula finally detaches, so take a careful history about when vision really changed.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteDemarcation Lines in Chronic Retinal Detachment
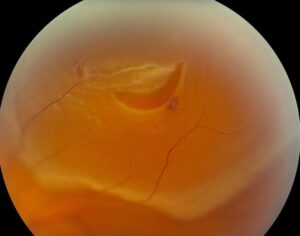
Pigmented demarcation lines, which clinicians call tidemarks or high-water marks, are a classic sign, and they form at the posterior edge of the detachment as RPE cells proliferate. Pigmentation generally takes about three months, according to standard texts, and multiple concentric lines suggest that the detachment advanced in stages. However, a line does not guarantee that fluid will stop there.
Intraretinal Cysts in Chronic Retinal Detachment
Intraretinal macrocysts appear as round, clear bubbles within the detached retina, and they usually develop in long-standing detachments, often after about a year. Their walls are thin, and they can mimic retinoschisis (see retinal cysts), but in most cases they collapse after reattachment, so they rarely need drainage.
Thin, Immobile Retina
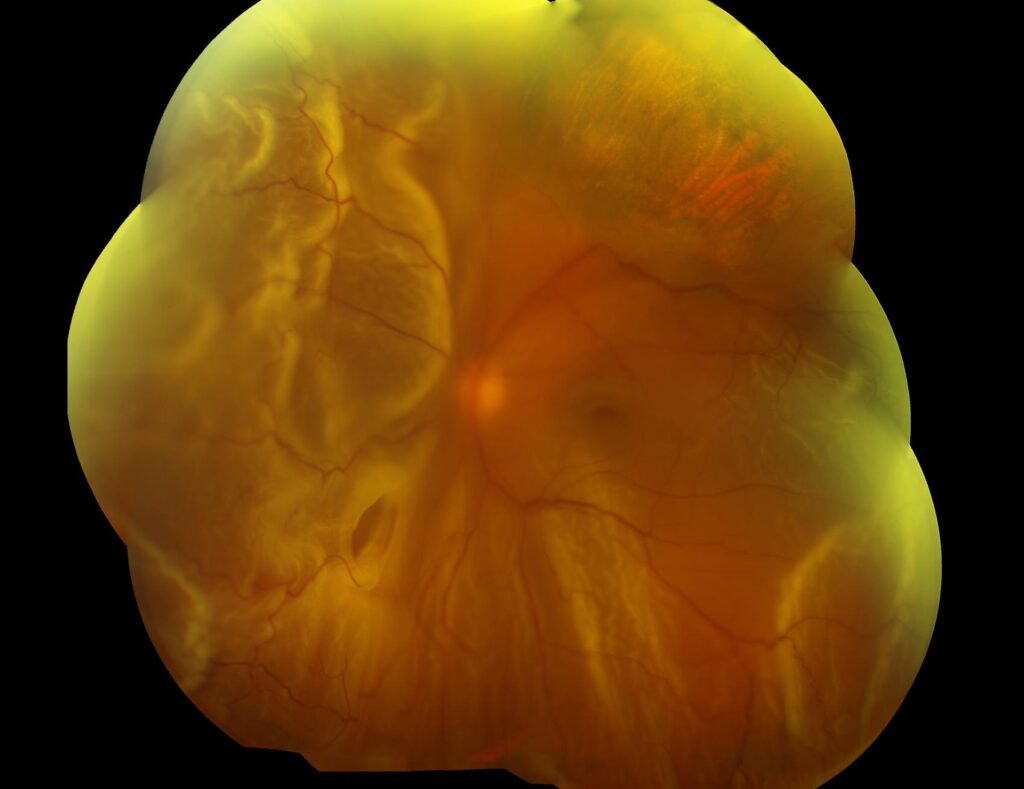
A fresh detachment looks convex, corrugated and mobile with eye movement, while a chronic detachment often looks thin, smooth and transparent. It moves little because the retina has atrophied and the fluid has become more viscous, so the examiner may underestimate its extent without careful indentation.
Subretinal Bands in Chronic Retinal Detachment
Subretinal fibrous bands look like white strands or branching lines beneath the retina, and sometimes they encircle the disc in a “napkin ring” pattern. Many bands do not block reattachment and can stay in place. However, a band that tents the retina may need surgical removal.
Other Clues to Duration
- Pigmented cells in the anterior vitreous (tobacco dust)
- Atrophic holes inside lattice degeneration
- Retinal dialysis with a rolled edge
- Low or raised intraocular pressure
- Cataract or iris neovascularization in very old detachments
- Proliferative vitreoretinopathy on the retinal surface
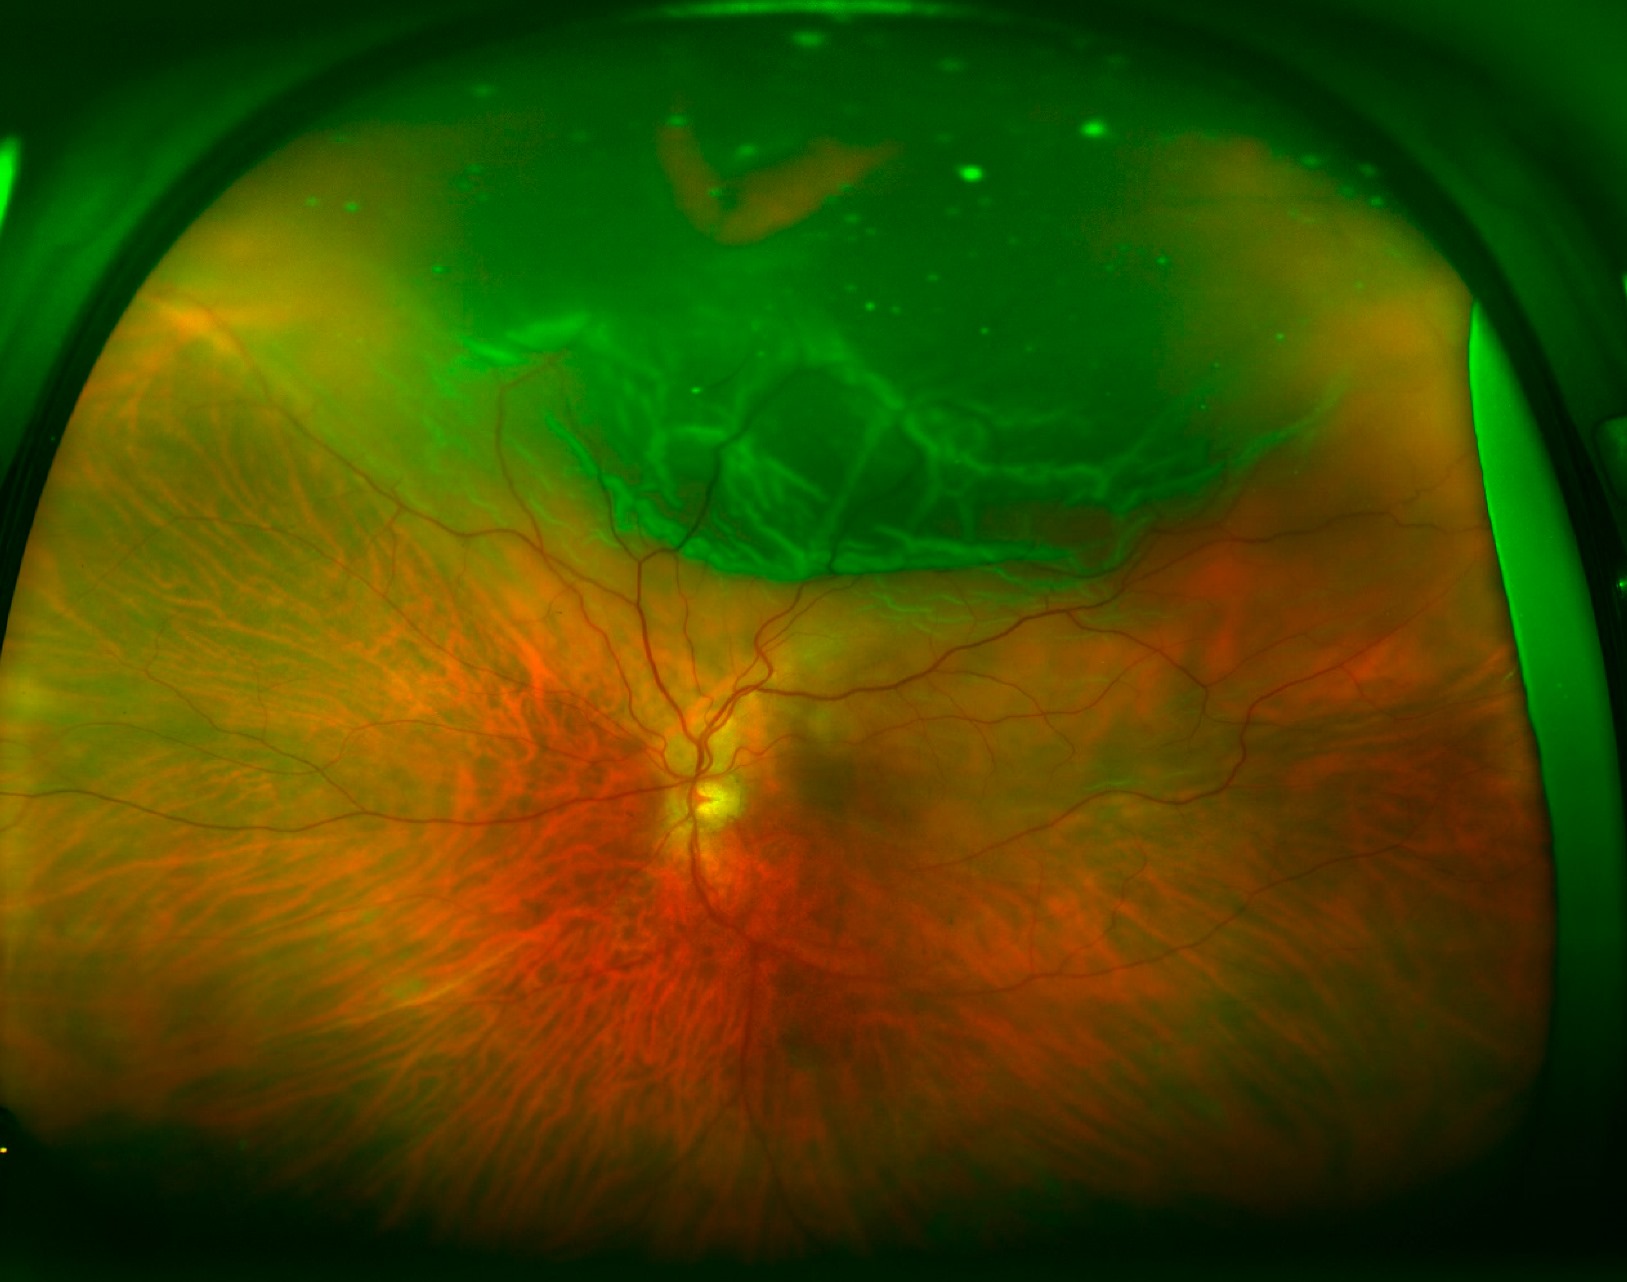
Pressure Changes
Most detached eyes run a lower pressure than the fellow eye. However, some chronic detachments raise the pressure as photoreceptor outer segments enter the aqueous. This pattern suggests Schwartz-Matsuo syndrome, especially with a dialysis, and pressure usually normalizes after successful repair.
Imaging Chronic Retinal Detachment
OCT shows a thin detached retina with outer retinal loss and intraretinal cystic spaces, and the subretinal fluid may appear more reflective than in a fresh detachment. B-scan ultrasound helps when cataract or hemorrhage blocks the view, and widefield photographs then document demarcation lines for follow-up.
Excluding Lookalikes
Degenerative retinoschisis is the main lookalike because it also looks smooth and immobile. However, schisis is often bilateral and dome shaped, without tobacco dust or pigmented lines, and you should also exclude exudative detachment, where fluid shifts with posture and no break exists.
Planning Repair of Chronic Retinal Detachment
Chronicity changes surgical priorities, and in young phakic eyes with an attached vitreous, scleral buckling remains a strong option. Drainage may help because chronic fluid is viscous and absorbs slowly. However, some surgeons buckle without drainage and accept slow resolution, and pockets of subretinal fluid can persist for months in young patients, but they usually resolve without further surgery.
Vitrectomy in Chronic Retinal Detachment
Vitrectomy suits eyes with posterior vitreous detachment, PVR or poor views, and the surgeon may need to peel membranes and occasionally perform a retinotomy. Advanced PVR may also require longer tamponade with silicone oil, and then the surgeon inspects subretinal bands and removes only those that prevent flattening.
Visual Prognosis in Chronic Retinal Detachment
Duration of macular detachment strongly predicts final acuity. After months off, photoreceptors may atrophy, so central vision often recovers only partly. However, repair still protects the remaining field and prevents further loss in many eyes, so discuss realistic goals before surgery (see macula-off retinal detachment).
Pitfalls to Avoid
- Do not assume a demarcation line will always contain the fluid
- Never mistake intraretinal cysts for retinoschisis or tumor
- Look for a retinal dialysis in any young patient with blunt trauma
- Avoid promising full central recovery after a long macula-off period


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Machemer R, Aaberg TM, Freeman HM, et al. An updated classification of retinal detachment with proliferative vitreoretinopathy. Am J Ophthalmol. 1991;112:159-165.
- Flaxel CJ, Adelman RA, Bailey ST, et al. Posterior Vitreous Detachment, Retinal Breaks, and Lattice Degeneration Preferred Practice Pattern. Ophthalmology. 2020;127:P146-P181.
- Salmon JF. Kanski’s Clinical Ophthalmology: A Systematic Approach. 9th ed. Elsevier; 2020.
- Schachat AP, Sadda SR, Hinton DR, et al, eds. Ryan’s Retina. 6th ed. Elsevier; 2018.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 12: Retina and Vitreous. San Francisco: AAO; 2023.
Test yourself
A few questions straight from this article.
-
Why can a chronic retinal detachment from atrophic lattice holes in a young myope creep for months without alarming symptoms?
In young myopes with atrophic lattice holes, and in trauma dialysis, the vitreous is usually attached, so fluid spreads slowly and the detachment can creep for months. -
A retinal dialysis after blunt trauma typically causes a slow chronic detachment in which quadrant?
A retinal dialysis after blunt trauma often causes a slow inferotemporal detachment, so look for a dialysis in any young patient with blunt trauma. -
According to standard texts, about how long does a demarcation line at the edge of a retinal detachment take to become pigmented?
Pigmented demarcation lines (tidemarks) form at the posterior edge of the detachment as RPE cells proliferate, and pigmentation generally takes about three months. -
How are intraretinal macrocysts in a long-standing retinal detachment usually managed?
Macrocysts appear as round clear bubbles, often after about a year of detachment; they can mimic retinoschisis but usually collapse after reattachment. -
How does a chronic retinal detachment typically look compared with a fresh one?
A fresh detachment is convex, corrugated and mobile, whereas a chronic one is thin, smooth and transparent and moves little because the retina has atrophied and the fluid is more viscous. -
In chronic retinal detachment, which subretinal fibrous bands may need surgical removal?
Many subretinal bands, including the 'napkin ring' around the disc, do not block reattachment and can stay; only a band that tents the retina or prevents flattening needs removal. -
A chronic retinal detachment with a dialysis shows raised intraocular pressure. Which mechanism and syndrome does this suggest?
Most detached eyes run lower pressure, but some chronic detachments raise it as photoreceptor outer segments enter the aqueous, suggesting Schwartz-Matsuo syndrome; pressure usually normalizes after repair. -
Which features favor degenerative retinoschisis over a chronic retinal detachment?
Schisis also looks smooth and immobile, but it is often bilateral and dome shaped without tobacco dust or pigmented lines; shifting fluid with no break suggests exudative detachment instead. -
Which repair remains a strong option for a chronic retinal detachment in a young phakic eye with an attached vitreous?
In young phakic eyes with an attached vitreous, scleral buckling remains a strong option, while vitrectomy suits eyes with posterior vitreous detachment, PVR or poor views. -
Which factor strongly predicts final visual acuity after repair of a chronic retinal detachment?
Duration of macular detachment strongly predicts final acuity, because photoreceptors may atrophy after months off, so central vision often recovers only partly.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.