Tear osmolarity testing measures the concentration of dissolved salts in the tears, and it is one of the objective tests used to support the diagnosis of dry eye.
Doctors regard hyperosmolarity as the central event in dry eye, so the measurement has a clear biological basis.
Its day-to-day variability is also the main problem, and the number should never be read alone.
Why Tear Osmolarity Testing Matters
In dry eye, tear evaporation rises or tear production falls, and the salt in the remaining tear film becomes more concentrated.
This hyperosmolar tear damages the surface cells, triggers inflammation, and reduces the stability of the tear film, which sustains a vicious cycle (see dry eye disease).
The test therefore targets the core mechanism of the disease, and does more than count a symptom.
Tear Osmolarity Testing: How the Test Is Done
Commercial devices use a few tens of nanoliters of tears collected from the lower lid margin with a small probe.
An electrical measurement gives a result in milliosmoles per liter within seconds.
- Test before any drops, a slit lamp light, or fluorescein, since they alter the tears
- Avoid touching the eye, and avoid reflex tearing, which dilutes the sample
- Wait for the patient to settle, and take the sample from the lateral lower lid meniscus
- Measure both eyes, and note the difference between them
Contact lens wear and recent drops may also give a falsely low or high reading.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteThresholds
Normal values average about 300 to 305 milliosmoles per liter.
In addition, the TFOS DEWS II diagnostic report suggests that a result of 308 or more in either eye, or a difference between the eyes of more than 8, supports a diagnosis of dry eye (see the references).
Also, higher values are linked to more severe disease, and a value above 316 is often taken as a marker of more severe dryness (see the references).
Tear Osmolarity Testing: Interocular Difference and Variability
A large difference between the two eyes reflects the instability of the tear film.
Healthy eyes show a small difference, while unstable surfaces have a greater swing from blink to blink.
This instability can also make a single measurement misleading, and some clinicians repeat the test or take the higher value of the two eyes.
What the Test Adds
- Objective support for the diagnosis when symptoms and signs are in conflict
- A measure of severity, with higher values in more severe disease
- A tool to follow treatment, as the osmolarity falls when the surface improves
- Help in selecting patients who might benefit from more intensive therapy (see meibomian gland dysfunction)
It is also used to test the surface before cataract and refractive surgery, since a hyperosmolar surface can affect biometry and outcome.
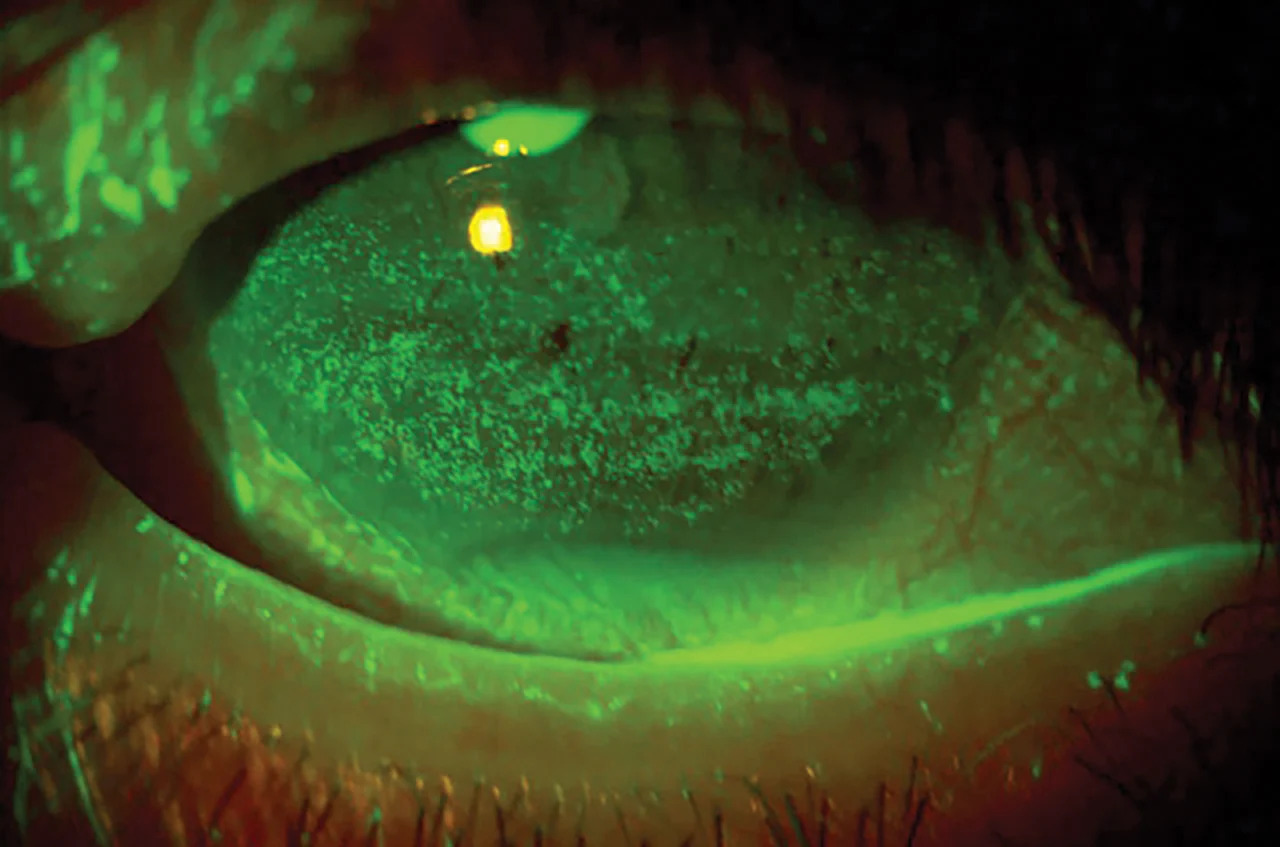
Limitations of Tear Osmolarity Testing
- Poor correlation with symptoms and some signs in several studies
- Variation with time of day, fluid in the tear meniscus, and reflex tearing
- Dependence on the technique, which affects the reading
- Cost of the device and disposable probes, which limits availability
- Normal values in some patients with dry eye symptoms, especially early disease
A normal result does not exclude dry eye, and an abnormal one does not prove it.
How to Use It in Practice
Combine the result with the symptom score, tear break-up time, corneal staining, and the lid and gland findings (see tear break-up time).
Interpret a borderline value with caution, and repeat the test if the picture is unclear.
Also, use the result to explain the problem to the patient, and to monitor the response.
An Example From the Clinic
A 55-year-old woman complains of burning and blur at the computer, with a short tear break-up time and mild staining.
Her osmolarity is 318 in the right eye and 305 in the left, a difference of 13, and the instability of the tear film is confirmed.
Treatment with lid care, preservative-free tears, and an anti-inflammatory drop is also started, and at three months the difference falls to 5 and the symptoms improve.
This shows how the number can support the plan and the follow-up.
Before Cataract and Refractive Surgery
Measuring osmolarity before biometry and keratometry helps to find an unstable surface that may give unreliable readings.
If the value is high, treat the surface and repeat the measurements after a few weeks, before choosing the lens power or the laser treatment (see dry eye after LASIK).
Choosing Other Tests to Combine
- Symptom questionnaires, such as the Ocular Surface Disease Index
- Tear break-up time and corneal and conjunctival staining
- Schirmer test for tear production (see Schirmer test)
- Lid margin and gland assessment


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Lemp MA, Bron AJ, Baudouin C, et al. Tear osmolarity in the diagnosis and management of dry eye disease. Am J Ophthalmol. 2011;151:792-798.
- Wolffsohn JS, Arita R, Chalmers R, et al. TFOS DEWS II diagnostic methodology report. Ocul Surf. 2017;15:539-574.
- Sullivan BD, Whitmer D, Nichols KK, et al. An objective approach to dry eye disease severity. Invest Ophthalmol Vis Sci. 2010;51:6125-6130.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 8: External Disease and Cornea. AAO; current edition.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.