
Post-vaccination uveitis describes intraocular inflammation that develops in the days to weeks after immunization, reported after a range of vaccines including influenza, hepatitis B, HPV, MMR, and COVID-19 vaccines.
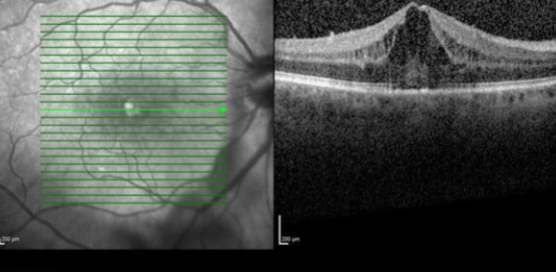
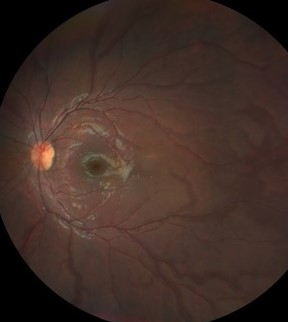
Post-vaccination uveitis is rare relative to the number of doses given, and a temporal association does not prove causation, but the pattern is consistent enough across reports to be recognized as a self-limited entity.
What Causes Post-Vaccination Uveitis?
The exact mechanism is not established.
Proposed explanations include molecular mimicry between vaccine antigens and ocular proteins, immune complex deposition, and nonspecific activation of the innate immune system by vaccine adjuvants.
None of these has been proven, and most patients have no other risk factor for uveitis.
Clinical Patterns
Reported presentations vary by vaccine type, though there is considerable overlap.
- Anterior uveitis, usually mild to moderate and often bilateral
- Multifocal choroiditis and panuveitis, reported after several vaccine types
- Vogt-Koyanagi-Harada-like presentations, with bilateral posterior uveitis and exudative detachment, reported rarely
- Episcleritis and scleritis, less common
- Optic neuritis and other neuro-ophthalmic events, which are managed separately from uveitis
Onset is typically within one to three weeks of vaccination, though later onset has been reported.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteEvaluation
The workup for suspected post-vaccination uveitis is the same as for uveitis of any cause, since the temporal link with a vaccine is a clue and not a diagnosis.
- A standard uveitis history and examination
- Testing for infectious and systemic causes appropriate to the anatomical pattern, since coincidental disease remains more likely than a vaccine reaction for most causes of uveitis
- OCT and fluorescein angiography as indicated by the pattern
- A clear record of the vaccine given and the interval to symptom onset, useful for pharmacovigilance reporting
A diagnosis of exclusion is reasonable once other causes have been reasonably ruled out and the timing is suggestive.
Management
Most cases are managed like uveitis from any other cause, using topical, periocular, or systemic corticosteroids depending on the anatomical location and severity.
There is no evidence that stopping a vaccine series or avoiding future vaccination is required for most patients, and this decision should involve the patient’s own physician and consider the benefit of the vaccine.
Recurrent uveitis after a subsequent dose of the same vaccine has been reported in a minority of cases, which is a reasonable factor to discuss before a booster if the earlier reaction was significant.
Reporting
Suspected vaccine-associated adverse events should be reported through the relevant national pharmacovigilance system.
Population-level surveillance, rather than individual case reports, is what will eventually clarify whether specific vaccines carry a measurable increase in uveitis risk.
Prognosis
Most reported cases resolve with standard uveitis treatment and do not recur unless the vaccine is repeated.
Severe or posterior presentations are less common but have the same visual risks as uveitis of any other cause and need the same urgency of treatment.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Benage M, Fraunfelder FW. Vaccine-associated uveitis. Mo Med. 2016;113:48-52.
- Ng XL, Betzler BK, Testi I, et al. Ocular adverse events after COVID-19 vaccination. Ocul Immunol Inflamm. 2021;29:1216-1224.
- Kim MJ, Yoon JM, Koh HJ, Lee SC. Vogt-Koyanagi-Harada disease after influenza vaccination. Korean J Ophthalmol. 2016;30:230-231.
- Ozdal PC, Ortac S, Taskintuna I, Firat E. Postvaccination uveitis with hepatitis B vaccine. Eur J Ophthalmol. 2002;12:350-352.
Test yourself
A few questions straight from this article.
-
Post-vaccination uveitis has been reported after which range of vaccines?
Intraocular inflammation after immunization has been described across a broad range of vaccines, including influenza, hepatitis B, HPV, MMR and COVID-19 vaccines, not one platform alone. -
Which mechanism has been proposed but not proven for post-vaccination uveitis?
The mechanism is not established. Proposed explanations include molecular mimicry between vaccine antigens and ocular proteins, immune complex deposition, and nonspecific innate immune activation by adjuvants. -
Anterior uveitis following vaccination is typically described as having which character?
Across reports, the anterior uveitis seen after vaccination is usually mild to moderate in severity and frequently affects both eyes. -
Which rare post-vaccination presentation features bilateral posterior uveitis with exudative detachment?
Vogt-Koyanagi-Harada-like presentations, with bilateral posterior uveitis and exudative retinal detachment, have been reported after vaccination but only rarely. -
Uveitis attributed to vaccination typically begins within which interval after the dose?
Onset is typically one to three weeks after immunization, although later onset has also been described. -
How should a temporal link to vaccination be treated when assessing new-onset uveitis?
A temporal association does not prove causation, so the evaluation is the same as for uveitis of any cause; coincidental disease remains more likely than a vaccine reaction for most causes. -
What is expected to clarify whether particular vaccines measurably raise uveitis risk?
Suspected events should be reported to national pharmacovigilance systems, and it is population-level surveillance rather than isolated case reports that will settle the question of risk. -
Post-vaccination uveitis is treated with which of the following approaches?
Management mirrors uveitis of any other cause: topical, periocular or systemic corticosteroids selected according to the anatomical location and the severity of inflammation. -
What is the stated position on completing a vaccine series after an episode of post-vaccination uveitis?
There is no evidence that most patients need to stop a vaccine series or avoid future immunization; the decision involves the patient's own physician and weighs the benefit of the vaccine. -
What is the usual outcome of reported cases of post-vaccination uveitis?
Reported cases generally settle with standard uveitis treatment and do not recur; recurrence after a further dose of the same vaccine has been described in a minority.
