Posterior scleritis is one of the more commonly missed causes of unexplained ocular pain, precisely because the anterior segment can look nearly normal while significant inflammation is occurring behind the equator, out of direct view of a routine slit-lamp examination.
Imaging is what turns the diagnosis from a guess into a confirmed finding, and B-scan ultrasonography is usually the fastest way to get there.
Why Posterior Scleritis Is Missed
Anterior scleritis announces itself with visible redness and scleral swelling that a patient and clinician can both see.
Posterior scleritis, by contrast, can present with severe pain, sometimes the worst symptom the patient reports, in an eye that looks quiet, mildly injected, or only subtly proptotic, so the diagnosis is easy to overlook unless it is specifically considered in the differential for unexplained ocular or periocular pain.
Clinical Features
- Pain, often significant, sometimes worse with eye movement, and frequently out of proportion to visible external findings
- Proptosis, from posterior scleral and episcleral swelling
- Restricted extraocular motility, sometimes mimicking an orbital process
- Reduced vision, from choroidal folds, exudative retinal detachment, macular edema, or optic disc swelling when the inflammation involves the posterior pole
- Eyelid edema in some patients
The combination of significant pain with a relatively quiet-looking anterior segment, particularly with any degree of proptosis or motility restriction, should raise suspicion for posterior scleritis rather than being dismissed as an unexplained headache or orbital complaint.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteImaging Findings
B-Scan Ultrasonography
B-scan is often the fastest and most accessible confirmatory test.
- Thickening of the posterior sclera and choroid
- The classic “T-sign,” in which fluid in the sub-Tenon space, outlined against the optic nerve shadow, creates a T-shaped pattern on ultrasound, a highly suggestive finding for posterior scleritis
- Associated findings such as choroidal detachment or exudative retinal detachment in more severe cases
CT and MRI
Orbital imaging shows scleral and episcleral thickening and can help exclude other causes of proptosis and pain, such as orbital cellulitis or idiopathic orbital inflammation, when the clinical picture is ambiguous.
Fundus Examination and OCT
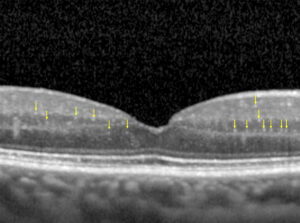
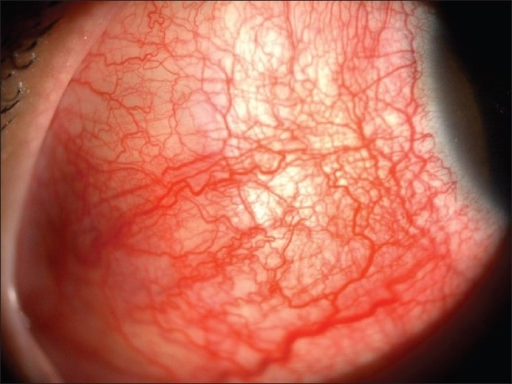
Direct examination and OCT can show choroidal folds, disc edema, macular edema, or serous retinal detachment when the posterior pole itself is involved, findings that help confirm posterior segment involvement and provide a baseline to monitor treatment response.
Differential Diagnosis
- Idiopathic orbital inflammation, which can produce a similar combination of pain and restricted motility but with a different pattern on imaging and typically without the T-sign (see idiopathic orbital inflammation)
- Orbital cellulitis, usually with more overt signs of infection and a source such as sinusitis
- Uveal effusion syndrome, which can share overlapping ultrasound and exudative detachment features but typically lacks the pain and scleral thickening pattern of active scleritis (see uveal effusion syndrome)
- Choroidal tumor, particularly when a mass-like thickening is present, excluded with careful imaging characterization
Systemic Workup
Posterior scleritis shares the same systemic disease associations as anterior scleritis and warrants the same evaluation, since it can be the presenting feature of an underlying systemic autoimmune disease just as anterior scleritis can (see scleritis classification).
- Rheumatoid factor and anti-CCP antibodies
- ANCA testing
- ANA and other connective tissue disease serology
- Infectious workup, including syphilis, when clinically indicated
Management
Treatment generally follows the same principles as anterior scleritis, guided by severity and any identified systemic association.
- Oral NSAIDs for milder cases
- Systemic corticosteroids for more significant inflammation, particularly with posterior segment involvement threatening vision
- Steroid-sparing immunosuppression for recurrent, severe, or systemic-disease-associated cases, coordinated with rheumatology
- Treatment of any identified underlying infectious or systemic autoimmune cause
Prognosis
With prompt recognition and appropriate treatment, most patients recover good vision and resolution of pain, though delayed diagnosis can allow complications such as exudative retinal detachment or macular edema to cause more lasting visual impairment.
The central lesson of posterior scleritis is that a normal-looking anterior segment does not rule out serious scleral inflammation, and B-scan ultrasonography is a quick, accessible way to look behind the part of the eye that can be seen directly.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Benson WE. Posterior scleritis. Surv Ophthalmol. 1988;32:297-316.
- McCluskey PJ, Watson PG, Lightman S, Haybittle J, Restori M, Branley M. Posterior scleritis: clinical features, systemic associations, and outcome in a large series of patients. Ophthalmology. 1999;106:2380-2386.
- Chaques-Alepuz V, Diaz-Valle D, Arriola-Villalobos P, Benitez-Del-Castillo JM. Posterior scleritis: descriptive study of the clinical presentation. Arch Soc Esp Oftalmol. 2014;89:293-297.
- Sainz de la Maza M, Molina N, Gonzalez-Gonzalez LA, Doctor PP, Tauber J, Foster CS. Clinical characteristics of a large cohort of patients with scleritis and episcleritis. Ophthalmology. 2012;119:43-50.
Test yourself
A few questions straight from this article.
-
What pain pattern is characteristic of posterior scleritis?
Posterior scleritis typically causes significant pain, sometimes worse with eye movement, and frequently out of proportion to the visible external findings. -
What produces the proptosis seen in posterior scleritis?
Proptosis in posterior scleritis arises from swelling of the posterior sclera and episclera. -
On B-scan in posterior scleritis, the T-shaped pattern is outlined against which structure?
Fluid in the sub-Tenon space, outlined against the optic nerve shadow, creates the T-shaped pattern on ultrasound that is highly suggestive of posterior scleritis. -
What does orbital CT or MRI contribute in suspected posterior scleritis?
Orbital imaging demonstrates scleral and episcleral thickening and helps exclude other causes of proptosis and pain, such as orbital cellulitis or idiopathic orbital inflammation. -
What role do fundus examination and OCT serve in posterior scleritis?
Direct examination and OCT can show choroidal folds, disc edema, macular edema or serous retinal detachment, confirming posterior segment involvement and providing a baseline for monitoring treatment response. -
Which imaging feature helps separate posterior scleritis from idiopathic orbital inflammation?
Idiopathic orbital inflammation can mimic posterior scleritis with pain and restricted motility, but it shows a different imaging pattern and typically lacks the T-sign. -
What distinguishes uveal effusion syndrome from posterior scleritis?
Uveal effusion syndrome can share ultrasound and exudative detachment features with posterior scleritis but typically lacks the pain and the scleral thickening pattern of active scleritis. -
How extensive should the systemic workup be in posterior scleritis?
Posterior scleritis shares the systemic disease associations of anterior scleritis and warrants the same evaluation, since it can be the presenting feature of underlying systemic autoimmune disease. -
What is appropriate initial treatment for milder posterior scleritis?
Treatment follows the same principles as anterior scleritis and is graded by severity, with oral NSAIDs used for milder cases and systemic corticosteroids reserved for more significant inflammation. -
What outcome is expected in posterior scleritis recognised and treated promptly?
With prompt recognition and appropriate treatment most patients recover good vision and their pain resolves, whereas delayed diagnosis allows exudative detachment or macular edema to cause lasting visual impairment.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.