Talc retinopathy is a distinctive crystalline maculopathy caused by intravenous injection of crushed oral medication tablets — most classically methylphenidate, amphetamine preparations, or other oral drugs diverted for illicit intravenous use — where the insoluble talc and cornstarch fillers used as binders in oral tablet manufacturing become embolized to the retinal circulation.
It is a genuinely useful sign for the examining ophthalmologist to recognize, since the retinal finding is essentially pathognomonic once seen and can be the first clue to a substance use history the patient has not otherwise disclosed.
Because most patients do not volunteer a history of intravenous drug misuse unprompted, and because the retinal particles themselves cause no discomfort, this finding is frequently discovered entirely by chance during a routine or unrelated eye exam rather than because the patient sought care for a visual complaint.
Mechanism
Oral tablets are formulated with insoluble particulate binders, fillers, and coating agents (talc and microcrystalline cellulose being classic examples) that are entirely appropriate for oral administration, where they simply pass through and are excreted by the gastrointestinal tract, but become a genuine embolic hazard when a crushed tablet is dissolved (often incompletely) and injected intravenously.
These insoluble particles travel through the venous circulation, through the right heart and pulmonary circulation, and — in patients with either a right-to-left cardiac shunt or, more commonly, simply enough particulate load over repeated injections to pass through the pulmonary capillary filter — reach the systemic arterial circulation and lodge in small-caliber vessels including the retinal arterioles.
Clinical Presentation
Many patients are asymptomatic, with the retinal findings discovered incidentally on a dilated fundus exam performed for another reason, since small numbers of retinal particles in the perifoveal region often do not significantly affect central vision.
With heavier, more longstanding particulate deposition, or with associated retinal ischemia and neovascularization (discussed below), patients can experience progressive, sometimes significant vision loss, which is generally what eventually prompts these patients to present for evaluation.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteExam Findings
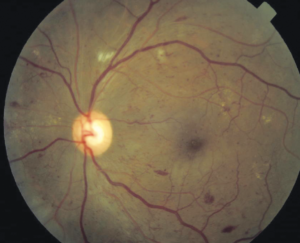
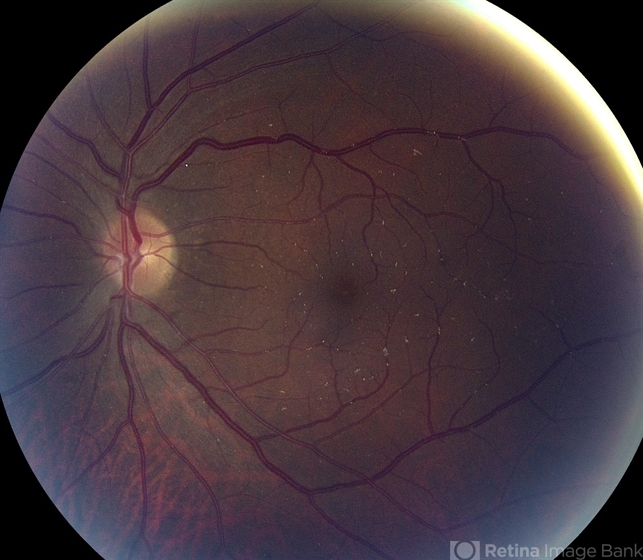
- Small, yellow-white, glistening, refractile particles scattered in the perifoveal and macular retinal vasculature, typically concentrated where the smallest retinal vessels are found — a distribution and appearance that is genuinely characteristic once recognized
- Particle density generally correlates with the cumulative history of intravenous drug use, though this is not a precise or reliable quantitative relationship
- Peripheral retinal capillary non-perfusion and ischemia in more advanced cases, related to chronic vascular occlusion from the embolized particles
- Retinal and, in severe cases, optic disc neovascularization, developing as a consequence of chronic retinal ischemia — analogous in mechanism to neovascularization from other ischemic retinal conditions discussed elsewhere on this site, though here driven by mechanical vascular occlusion from foreign particulate material rather than a primary vascular disease process
- Vitreous hemorrhage, when neovascular vessels bleed, following the same general mechanism and management considerations as vitreous hemorrhage from any other ischemic retinal cause, discussed in this site’s dedicated coverage of that condition
Differential Diagnosis
- Canthaxanthin retinopathy — also causes a crystalline maculopathy, but from oral dietary supplement use rather than intravenous injection, with a distinct, more ring-like distribution of crystals and no associated ischemic or neovascular risk, discussed in its own dedicated article on this site
- Bietti crystalline dystrophy — an inherited crystalline retinal dystrophy, distinguished by its genetic basis, bilateral symmetric distribution, and lack of any relevant drug use history
- Calcific or cholesterol emboli (Hollenhorst plaque) — typically fewer, larger, and located at arterial bifurcations, related to carotid or cardiac embolic disease rather than the numerous, fine, diffusely scattered particles typical of talc retinopathy
- Other causes of retinal ischemia and neovascularization (diabetic retinopathy, retinal vein occlusion) — distinguished by the absence of the characteristic crystalline particles and by their own distinct, relevant clinical context
Diagnostic and Clinical Significance
Recognizing talc retinopathy carries significance well beyond the eye finding itself, since it is direct, objective evidence of intravenous drug use that the patient may not have volunteered, and it should prompt a broader, non-judgmental conversation about substance use, screening for associated infectious risks (HIV, hepatitis B and C, endocarditis), and, where appropriate, referral to addiction medicine or harm-reduction services.
The finding is, in a genuine sense, a systemic health sentinel discovered through a routine eye exam, not merely an isolated retinal curiosity.
Handled sensitively, this conversation can genuinely open the door to addiction treatment for a patient who had not otherwise engaged with the healthcare system around their substance use, making the ophthalmologist’s role here extend well beyond simply documenting and monitoring the eye finding.
Management
There is no treatment that removes already-embolized retinal particles; management focuses on addressing the underlying substance use (ideally through referral to appropriate addiction treatment resources) to prevent further embolic burden, and on monitoring for and treating the ischemic and neovascular complications when they develop.
Retinal neovascularization from talc retinopathy is managed with the same general approach used for neovascularization from any ischemic retinal cause — panretinal photocoagulation and, where indicated, anti-VEGF therapy, following the principles discussed in this site’s broader coverage of ischemic retinal disease and neovascular complications.
Because ongoing intravenous drug use continues to add new particulate burden over time, achieving durable stabilization of the ischemic and neovascular complications depends heavily on successfully addressing the underlying substance use rather than treating each neovascular episode as an isolated event.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Atlee WE Jr. Talc and cornstarch emboli in eyes of drug abusers. JAMA.
- Tse DT, Ober RR. Talc retinopathy. American Journal of Ophthalmology.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 12: Retina and Vitreous.
Test yourself
A few questions straight from this article.
-
What causes talc retinopathy?
Talc retinopathy is a crystalline maculopathy caused by injecting crushed oral tablets intravenously, so that the insoluble binders used in tablet manufacture embolise to the retinal circulation. -
Which drugs are most classically implicated in talc retinopathy?
Methylphenidate and amphetamine preparations are the drugs most classically diverted from oral use and injected intravenously in talc retinopathy. -
How do injected tablet filler particles reach the retinal arterioles in talc retinopathy?
Particles travel through the venous circulation and right heart, then reach the systemic arterial circulation either through a right-to-left shunt or, more commonly, by overwhelming the pulmonary capillary filter with repeated injections. -
Which fundus finding is characteristic of talc retinopathy?
Small, yellow-white, glistening refractile particles scattered through the perifoveal and macular vasculature, concentrated in the smallest retinal vessels, are the characteristic finding. -
How is talc retinopathy most often discovered?
Many patients are asymptomatic because small numbers of perifoveal particles do not greatly affect central vision, so the finding usually turns up by chance on a dilated exam. -
Which sequence of complications can follow heavy particulate deposition in talc retinopathy?
Chronic occlusion by embolised particles produces peripheral capillary non-perfusion and ischaemia, which drives retinal and sometimes disc neovascularisation, and those vessels can bleed into the vitreous. -
Which feature distinguishes canthaxanthin retinopathy from talc retinopathy?
Canthaxanthin retinopathy follows oral dietary supplement use rather than intravenous injection, shows a more ring-like crystal distribution, and carries no associated ischaemic or neovascular risk. -
Which feature distinguishes Hollenhorst plaques from the particles of talc retinopathy?
Calcific or cholesterol emboli are typically fewer, larger and sited at arterial bifurcations, reflecting carotid or cardiac embolic disease, unlike the numerous fine particles of talc retinopathy. -
What should recognising talc retinopathy prompt beyond ocular care?
The finding is objective evidence of intravenous drug use and should prompt a non-judgmental conversation, screening for HIV, hepatitis B and C and endocarditis, and referral to addiction or harm-reduction services. -
How is retinal neovascularisation arising from talc retinopathy managed?
Neovascularisation here is treated like that from any ischaemic retinal cause, with panretinal photocoagulation and anti-VEGF where indicated, while durable control depends on addressing the underlying drug use.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.