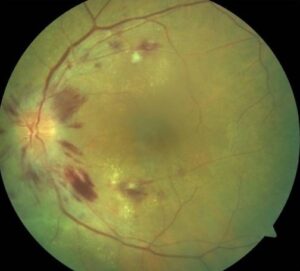
Black sunburst is a flat, pigmented chorioretinal scar in the peripheral fundus of patients with sickle hemoglobinopathies.
It usually marks the late stage of an earlier retinal hemorrhage.
Therefore, it records past vascular occlusion and rarely threatens vision directly.
However, it should prompt a careful search for proliferative disease elsewhere in the periphery.
What a Black Sunburst Looks Like
The lesion appears round or oval, black or dark brown, with spiculated margins.
Those stellate edges give the sign its name.
In addition, small refractile spots may sit within or beside the pigment.
Where the Lesion Sits
Most lesions lie near the equator or in the midperiphery, often close to a retinal arteriole.
Because they typically spare the macula, patients rarely report symptoms.
As a result, clinicians usually find them during routine dilated screening.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteHow Black Sunburst Evolves From Hemorrhage
The sequence starts when sickled erythrocytes occlude a peripheral arteriole.
The weakened vessel wall may then rupture and bleed into the retina.
Fresh blood forms a salmon patch, which turns from red to orange as hemoglobin breaks down.
Next, the blood may resorb and leave a schisis cavity with iridescent deposits.
Alternatively, blood can dissect beneath the sensory retina and irritate the pigment epithelium.
The epithelium then proliferates and migrates, and a black sunburst forms.
However, clinicians do not witness a preceding hemorrhage in every patient.
Histology of the Pigmented Scar
Histopathology shows hyperplasia and hypertrophy of the retinal pigment epithelium, with pigment migration into the retina.
Hemosiderin-laden macrophages may also persist, which may explain some refractile granules.
Fluorescein Angiography in Black Sunburst
Dense pigment blocks background choroidal fluorescence, so the center looks dark.
Meanwhile, window defects may appear where the epithelium has atrophied.
The scar itself should not leak.
Therefore, late leakage nearby suggests neovascularization and deserves close inspection.
Ultra-widefield angiography also maps peripheral nonperfusion, which often tells you more about risk than the scar does.
OCT Findings
OCT of a peripheral lesion can be technically difficult.
When captured, it may show hyperreflective pigment at the epithelial level with shadowing below.
In addition, OCT helps separate a flat scar from an elevated choroidal mass.
Black Sunburst and Sickle Genotype
The sign occurs across sickling hemoglobinopathies, including HbSS and HbSC disease.
Proliferative retinopathy is more frequent in HbSC and sickle thalassemia than in HbSS.
Therefore, request hemoglobin testing when the systemic diagnosis is unknown.
Black Sunburst in the Goldberg Classification
Goldberg’s staging describes proliferative disease, from peripheral arteriolar occlusion to retinal detachment.
Black sunburst belongs to nonproliferative sickle retinopathy and has no stage of its own.
Therefore, stage the eye by its perfusion border, anastomoses and any sea fans.
Differential Diagnosis
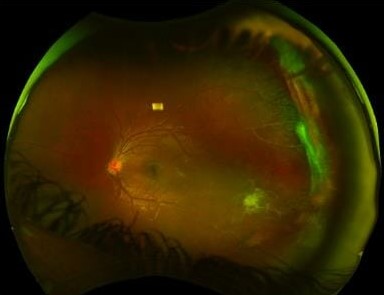
Several pigmented fundus lesions can mimic this scar, so history and morphology both help.
- Congenital hypertrophy of the RPE: sharp borders, lacunae, often a halo
- Choroidal nevus: slate gray, deep, with soft margins
- Choroidal melanoma: elevated mass, orange pigment, subretinal fluid
- Old chorioretinitis or traumatic scar: relevant history, atrophy with pigment
- Laser scars: regular pattern and treatment history
When to Worry About a Pigmented Lesion
Elevation, subretinal fluid, orange pigment or documented growth do not fit this diagnosis.
These features call for ocular oncology assessment with ultrasound.
Baseline photographs also help with any pigmented lesion, as they do with an episcleral nevus.
Does Black Sunburst Need Treatment?
The scar itself needs no treatment.
Laser, injections and surgery have no established role, because the lesion is inactive and usually asymptomatic.
Also, no therapy can remove the pigment or restore retina lost to ischemia.
By contrast, submacular hemorrhage threatens photoreceptors directly and follows a different management pathway.
Treating Associated Proliferative Disease
Management changes when the examination reveals sea fan neovascularization.
Scatter peripheral laser can promote regression, although some sea fans autoinfarct spontaneously.
Therefore, many specialists individualize treatment, weighing bilateral disease, growth, bleeding and access to follow-up.
Anti-VEGF injections have seen off-label use, but controlled evidence remains limited.
Follow-Up After Finding a Black Sunburst
Examine both eyes with dilation and record the lesion with widefield color photography.
Then review the perfusion border and look for neovascularization at each visit.
Many clinicians examine asymptomatic patients annually, although published intervals vary.
Counseling Patients With Black Sunburst
Explain that the spot is usually an old scar from a past bleed.
It rarely affects vision, and it needs no procedure.
However, it confirms that sickle disease has affected the retinal circulation.
Therefore, advise regular eye visits even without symptoms.
New floaters, flashes or a curtain need same-day assessment.
Pitfalls to Avoid
- Avoid calling a flat scar melanoma before checking margins and elevation
- Never stop at the scar, because sea fans may lie nearby
- Do not treat the pigment with laser
For the latest studies, see the PubMed results for black sunburst.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Goldberg MF. Classification and pathogenesis of proliferative sickle retinopathy. Am J Ophthalmol. 1971;71:649-665.
- Asdourian G, Nagpal KC, Goldbaum M, et al. Evolution of the retinal black sunburst in sickling haemoglobinopathies. Br J Ophthalmol. 1975;59:710-716.
- Gagliano DA, Goldberg MF. The evolution of salmon-patch hemorrhages in sickle cell retinopathy. Arch Ophthalmol. 1989;107:1814-1815.
- Romayanada N, Goldberg MF, Green WR. Histopathology of sickle cell retinopathy. Trans Am Acad Ophthalmol Otolaryngol. 1973;77:OP652-OP676.
- Elagouz M, Jyothi S, Gupta B, Sivaprasad S. Sickle cell disease and the eye: old and new concepts. Surv Ophthalmol. 2010;55:359-377.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.