
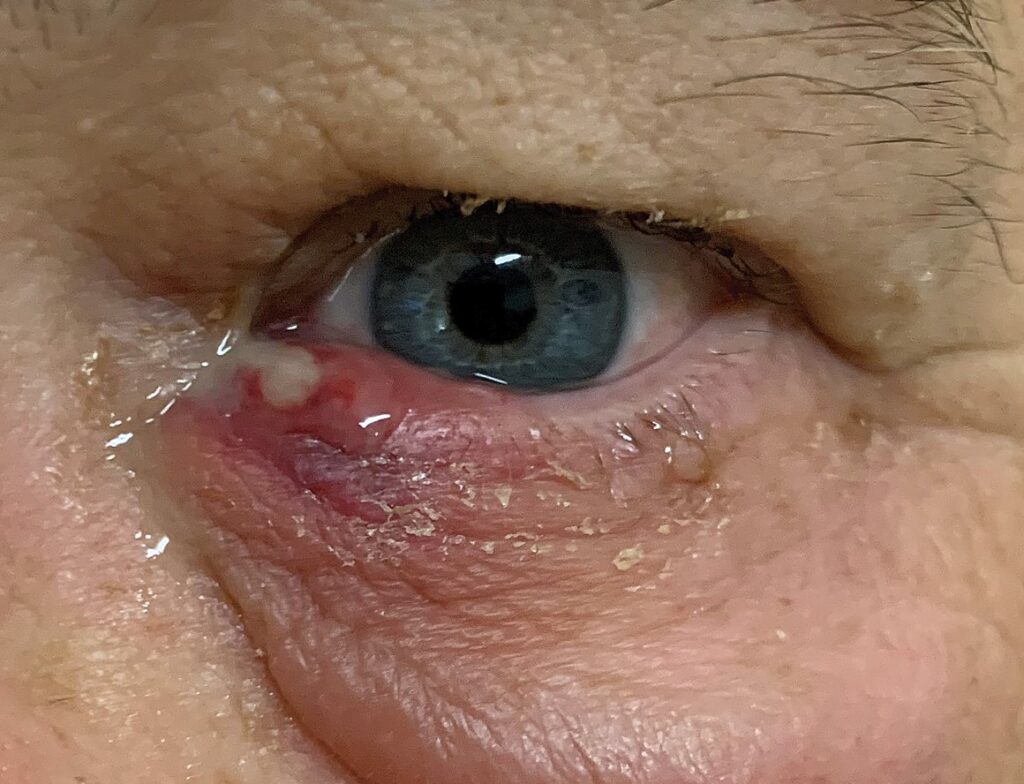
Dacryocystorhinostomy is an operation that makes a new passage for tears between the lacrimal sac and the nose.
It is also the standard treatment for acquired obstruction of the nasolacrimal duct that causes constant tearing or repeated infection.
Success rates are high when surgeons select the patient carefully and understand the anatomy.
When Is Dacryocystorhinostomy Needed?
- Epiphora from an acquired obstruction below the level of the lacrimal sac
- Recurrent dacryocystitis or a lacrimal sac mucocele (see dacryocystitis)
- Failed probing or intubation in a child with a persistent congenital obstruction (see congenital nasolacrimal duct obstruction)
- Chronic infection that threatens intraocular surgery, since a dacryocystitis increases the risk of endophthalmitis
- Traumatic obstruction of the duct or the sac
The operation does not help tearing from canalicular blockage, lid laxity, or dry eye, so exclude them first.
Preoperative Assessment
- A history of the amount of tearing, discharge, and infections
- Examination of the lids, puncta, and the lacrimal sac, with attention to a lid malposition
- Syringing and probing, which locate the level of the block, with a hard stop and reflux through the opposite punctum in a sac or duct obstruction
- Dacryocystography or CT in complex cases, trauma, and tumors
- An assessment of the nose, since a deviated septum, polyps, or rhinitis may affect surgery
Patients with a canalicular block above the sac need a different approach, such as a bypass tube.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteExternal Dacryocystorhinostomy
The classic method uses a skin incision on the side of the nose.
- The surgeon exposes the lacrimal sac and makes a bony window in the lacrimal fossa
- Next, the surgeon opens the nasal mucosa and the sac wall and sutures them together as flaps, to create a wide anastomosis
- Surgeons sometimes place silicone tubes through the canaliculi into the nose and leave them for weeks to months
- Surgeons close the wound in layers
In addition, success rates are generally 90 to 95 percent in published series, which makes it the benchmark (see the references).
Its drawbacks are also a scar on the face, a longer operation, and more bleeding.
Endonasal Dacryocystorhinostomy
- Clinicians perform the procedure through the nose with an endoscope, without a skin incision
- The surgeon removes bone over the sac with a drill or punch and opens the sac into the nose
- Some surgeons use intubation and mitomycin C
Success rates are slightly lower in some early series, around 80 to 90 percent, but modern results are close to those of the external approach, with faster recovery and no scar (see the references).
It requires endoscopic skills and works best in a team with an ear, nose, and throat surgeon.
Adjuncts
- Silicone intubation: keeps the new opening patent while it heals, and surgeons remove it after a few weeks to months
- Mitomycin C: reduces scarring at the ostium, though it is not used by all
- Laser-assisted methods: have shown variable success
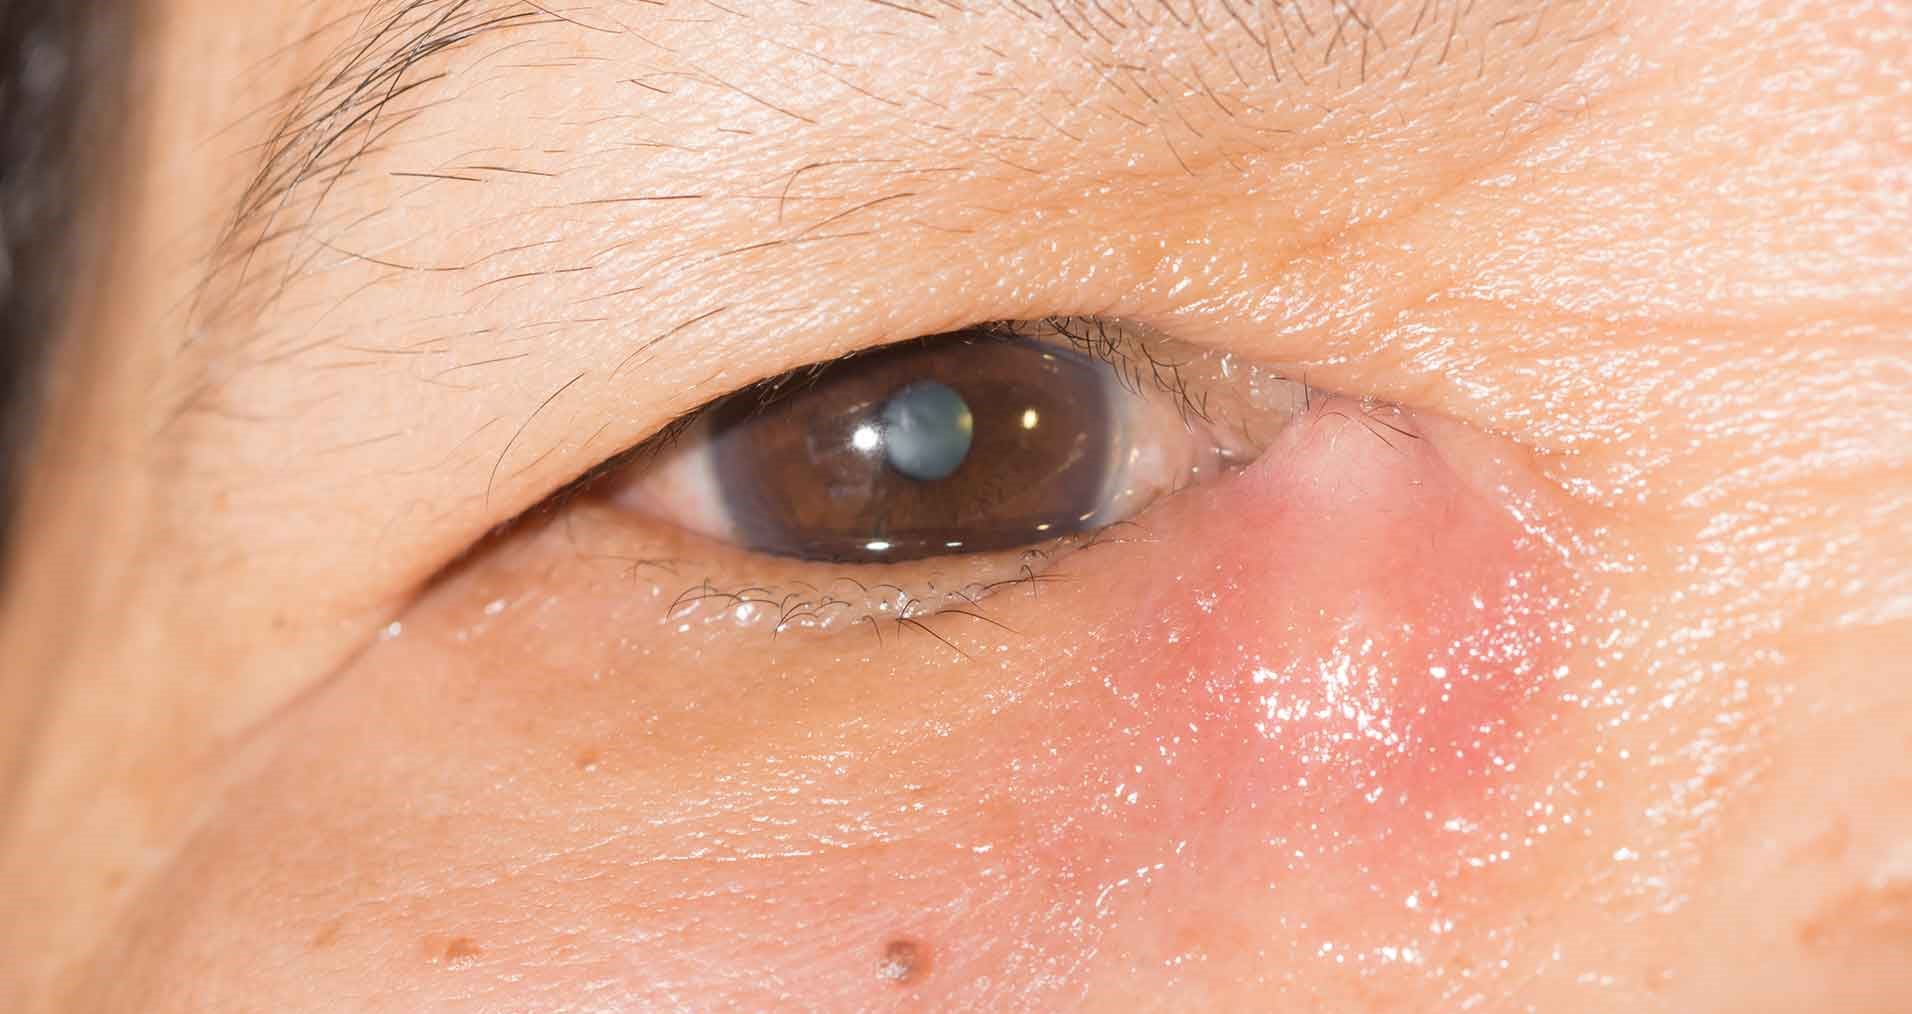
Complications of Dacryocystorhinostomy
- Bleeding, in particular in patients with hypertension or anticoagulants
- Failure from closure of the ostium by scar tissue, granuloma, or a retained flap
- Infection and wound problems
- Medial canthal scar and webbing after external surgery
- Rare injury to the orbit, cerebrospinal fluid leak, or damage to the canaliculi
The most common reason for failure is a scarred or narrowed ostium, and revision is possible.
Postoperative Care
- Antibiotic and steroid drops, and nasal steroid spray or saline rinses
- Avoid blowing the nose hard for a couple of weeks
- Review at one week and after a month, with syringing and endoscopy where needed
- Remove the tubes at the planned time
Counselling
Explain that the operation improves tearing in most patients, and that some may have a little residual watering.
Also, tell them the reasons for each step, and the plan for follow-up.
Choosing Between the Approaches
- Choose the external route when the sac is scarred, small, or the anatomy is difficult, and when the surgeon has more experience with it
- Choose the endonasal route in patients who wish to avoid a scar, those on anticoagulants who may also bleed less with an endoscopic approach, and in revisions
- Combine the endonasal approach with a lacrimal bypass tube in canalicular disease
Revision Surgery
If symptoms return, endoscopy shows whether the ostium is closed, narrowed, or covered by a flap.
Revision can reopen the ostium, with the use of mitomycin C and intubation, and many patients improve (see phacoemulsification for the timing before eye surgery in patients with chronic sac infection).
Look carefully for missed causes, such as canalicular stenosis or lid laxity, before repeating the operation.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Tarbet KJ, Custer PL. External dacryocystorhinostomy: surgical success, patient satisfaction, and economic cost. Ophthalmology. 1995;102:1065-1070.
- Hartikainen J, Antila J, Varpula M, et al. Prospective randomized comparison of endonasal endoscopic dacryocystorhinostomy and external dacryocystorhinostomy. Laryngoscope. 1998;108:1861-1866.
- Ben Simon GJ, Joseph J, Lee S, Schwarcz RM, McCann JD, Goldberg RA. External versus endoscopic dacryocystorhinostomy for acquired nasolacrimal duct obstruction in a tertiary referral center. Ophthalmology. 2005;112:1463-1468.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 7: Oculofacial Plastic and Orbital Surgery. AAO; current edition.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.


