UKPDS and ACCORD Eye are the two main trial programs that tested systemic treatment to protect the retina in type 2 diabetes.
Also, the UK Prospective Diabetes Study showed that tight glucose and blood pressure control reduce microvascular disease, and ACCORD Eye added a surprise, the benefit of fenofibrate.
In addition, together they give ophthalmologists clear points to discuss with the physician.
Why UKPDS and ACCORD Eye Were Needed
The DCCT studied type 1 diabetes, and it was not clear that its lessons applied to older patients with insulin resistance (see DCCT and EDIC).
Type 2 patients also have high blood pressure and lipid problems, which affect the retina.
UKPDS and ACCORD Eye: UKPDS Glucose Control
The UKPDS enrolled 3,867 patients with newly diagnosed type 2 diabetes, and compared intensive treatment with sulfonylureas or insulin to conventional diet-based treatment.
- Intensive control lowered HbA1c by about 0.9 percent
- It reduced microvascular complications by about 25 percent
- It reduced the need for retinal photocoagulation, mainly after nine years (see the references)
Metformin in overweight patients reduced diabetes-related endpoints, though its effect on the retina was less clear.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteUKPDS Blood Pressure Control
UKPDS 38 randomized hypertensive patients to tight blood pressure control, with a mean of 144/82, or less tight control, with a mean of 154/87.
- Tight control reduced microvascular complications by 37 percent
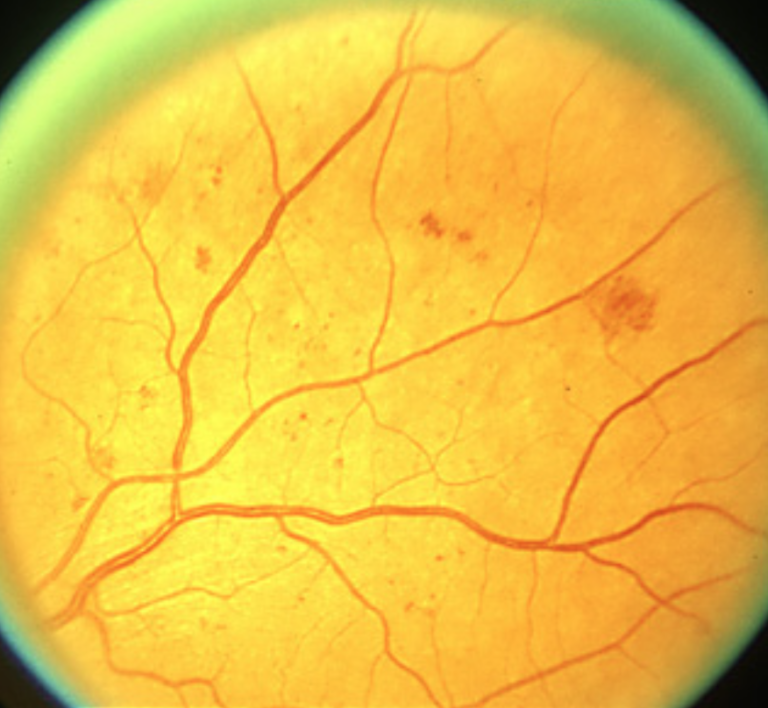
- It reduced the progression of retinopathy by about a third at 7.5 years. The risk of a three-line loss of vision by 47 percent (see the references)
In addition, the benefit was independent of the drug used.
UKPDS and ACCORD Eye: ACCORD Eye Design
ACCORD Eye was a substudy of the ACCORD trial in patients with type 2 diabetes at high cardiovascular risk.
It had three comparisons in 2,856 participants.
- Intensive versus standard glycemic control, with HbA1c of below 6 percent versus 7 to 7.9 percent
- Fenofibrate plus simvastatin versus simvastatin alone
- Intensive versus standard blood pressure control
Also, the main outcome was progression of retinopathy by three or more steps on the ETDRS scale, or treatment for the disease at four years.
ACCORD Eye Results
- Intensive glycemic control reduced progression, about 7.3 percent versus 10.4 percent
- Fenofibrate with simvastatin reduced progression by about 40 percent, 6.5 percent versus 10.2 percent
- Intensive blood pressure control did not reduce progression (see the references)
The intensive glycemic arm of the main ACCORD trial was stopped early for increased mortality, so the strategy was not adopted widely for older patients with heart disease.
UKPDS and ACCORD Eye: What Changed in Practice
- Control of glucose and blood pressure is also part of eye care, with attention to safety in older patients
- Clinicians consider fenofibrate in patients with diabetic retinopathy, and several countries have approved it, with data from other trials (see fenofibrate and diabetic retinopathy)
- Rapid improvement of glucose should also be accompanied by an eye exam
Limits
Also, the trials were done before the newer drug classes, such as GLP-1 agonists, which raise their own questions (see GLP-1 agonists and diabetic retinopathy).
Also, ACCORD participants were at high cardiovascular risk, and the results may not apply to every patient.
UKPDS and ACCORD Eye: Counselling
Explain that retinopathy is partly a disease of the whole body, and that the diabetes physician, the eye doctor, and the patient share the work.
In addition, encourage regular screening, blood pressure control, and adherence to medicines.
How the Findings Fit Together
The three lessons are that glucose control slows retinopathy, that blood pressure control protects the small vessels, and that lipid-lowering with fenofibrate may add benefit beyond statins (see diabetic retinopathy).
Each applies to a different group, and the best plan is also individual.
Practical Points for the Eye Clinic
- Ask about the latest HbA1c, blood pressure, and lipid values at each visit
- Write to the physician when retinopathy progresses despite reported control, and when severe disease appears
- Advise patients not to stop fenofibrate or other drugs on their own
- Reinforce that smoking cessation helps the vessels of the eye
Limits of the Evidence
ACCORD Eye enrolled a high-risk population and followed patients for four years.
Some benefits might differ in a longer or lower-risk population.
The fenofibrate result was later supported by other trials, but the evidence is still being updated.
Cooperation Between Specialists
The best results come when the eye doctor, the diabetes physician, and the primary care doctor share data and goals, so a short note after each eye visit is useful.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- UK Prospective Diabetes Study (UKPDS) Group. Intensive blood-glucose control with sulphonylureas or insulin compared with conventional treatment and risk of complications in patients with type 2 diabetes (UKPDS 33). Lancet. 1998;352:837-853.
- UK Prospective Diabetes Study Group. Tight blood pressure control and risk of macrovascular and microvascular complications in type 2 diabetes: UKPDS 38. BMJ. 1998;317:703-713.
- ACCORD Study Group; ACCORD Eye Study Group. Effects of medical therapies on retinopathy progression in type 2 diabetes. N Engl J Med. 2010;363:233-244.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 12: Retina and Vitreous. AAO; current edition.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.