Iris pigment epithelial cysts are, by a wide margin, the most frequently encountered type of iris cyst in routine clinical practice, and most of the clinical work involved in managing them well is really about confirming, confidently and efficiently, that a given lesion fits this specific, reliably benign pattern rather than something requiring closer attention.
Where These Cysts Arise
These cysts originate from the posterior pigment epithelial layer of the iris, the deeply pigmented layer lining the back surface of the iris, and they can occur at several characteristic locations along the iris, each with slightly different typical behavior and implications.
Location-Based Patterns
Pupillary Margin Cysts
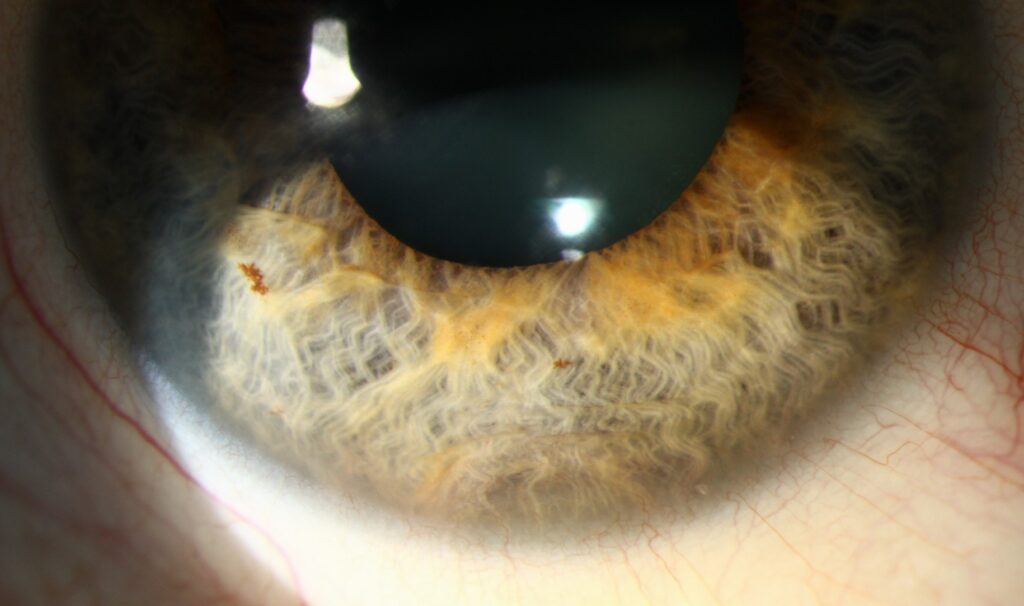
Located at the pupillary border, these are often visible as a small, darkly pigmented bulge at the pupil edge, and while they can occasionally be mistaken for a solid pigmented lesion at first glance, their cystic nature is usually readily confirmed with transillumination.
Mid-Zonal (Iris Stroma-Overlying) Cysts
Located in the mid-portion of the iris, these cysts can sometimes be large enough to cause visible iris elevation, though they remain confined to the posterior pigment epithelial origin rather than representing a stromal process.
Peripheral (Iridociliary) Cysts
Located near the iris root, these cysts can extend into or be more closely associated with the ciliary body region, sometimes overlapping conceptually with the broader category of ciliary body cysts discussed separately (see ciliary body cyst for the related discussion of cysts arising more posteriorly).
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteClinical Features
- Typically discovered incidentally during routine examination, particularly with pupillary dilation, which can reveal a cyst that was not apparent with the pupil in its normal, constricted state
- Generally stable in size over long-term follow-up, one of the most reassuring and clinically useful features of this specific cyst type
- Usually asymptomatic, though larger cysts occasionally cause mild visual symptoms related to mechanical effects on the pupil or, rarely, induced astigmatism
- Can be single or multiple, and bilateral involvement occurs in some patients
Confirming the Diagnosis
- Transillumination is a simple, reliable bedside technique for confirming the cystic, fluid-filled nature of these lesions, since light readily passes through a cyst and appears as a bright, translucent glow, in clear contrast to the shadow a solid lesion would produce (see iris cyst classification for the broader discussion of this and other distinguishing techniques)
- Ultrasound biomicroscopy provides more detailed structural confirmation when needed, though for a typical, classically appearing and positioned iris pigment epithelial cyst, transillumination alone is often sufficient for confident clinical diagnosis
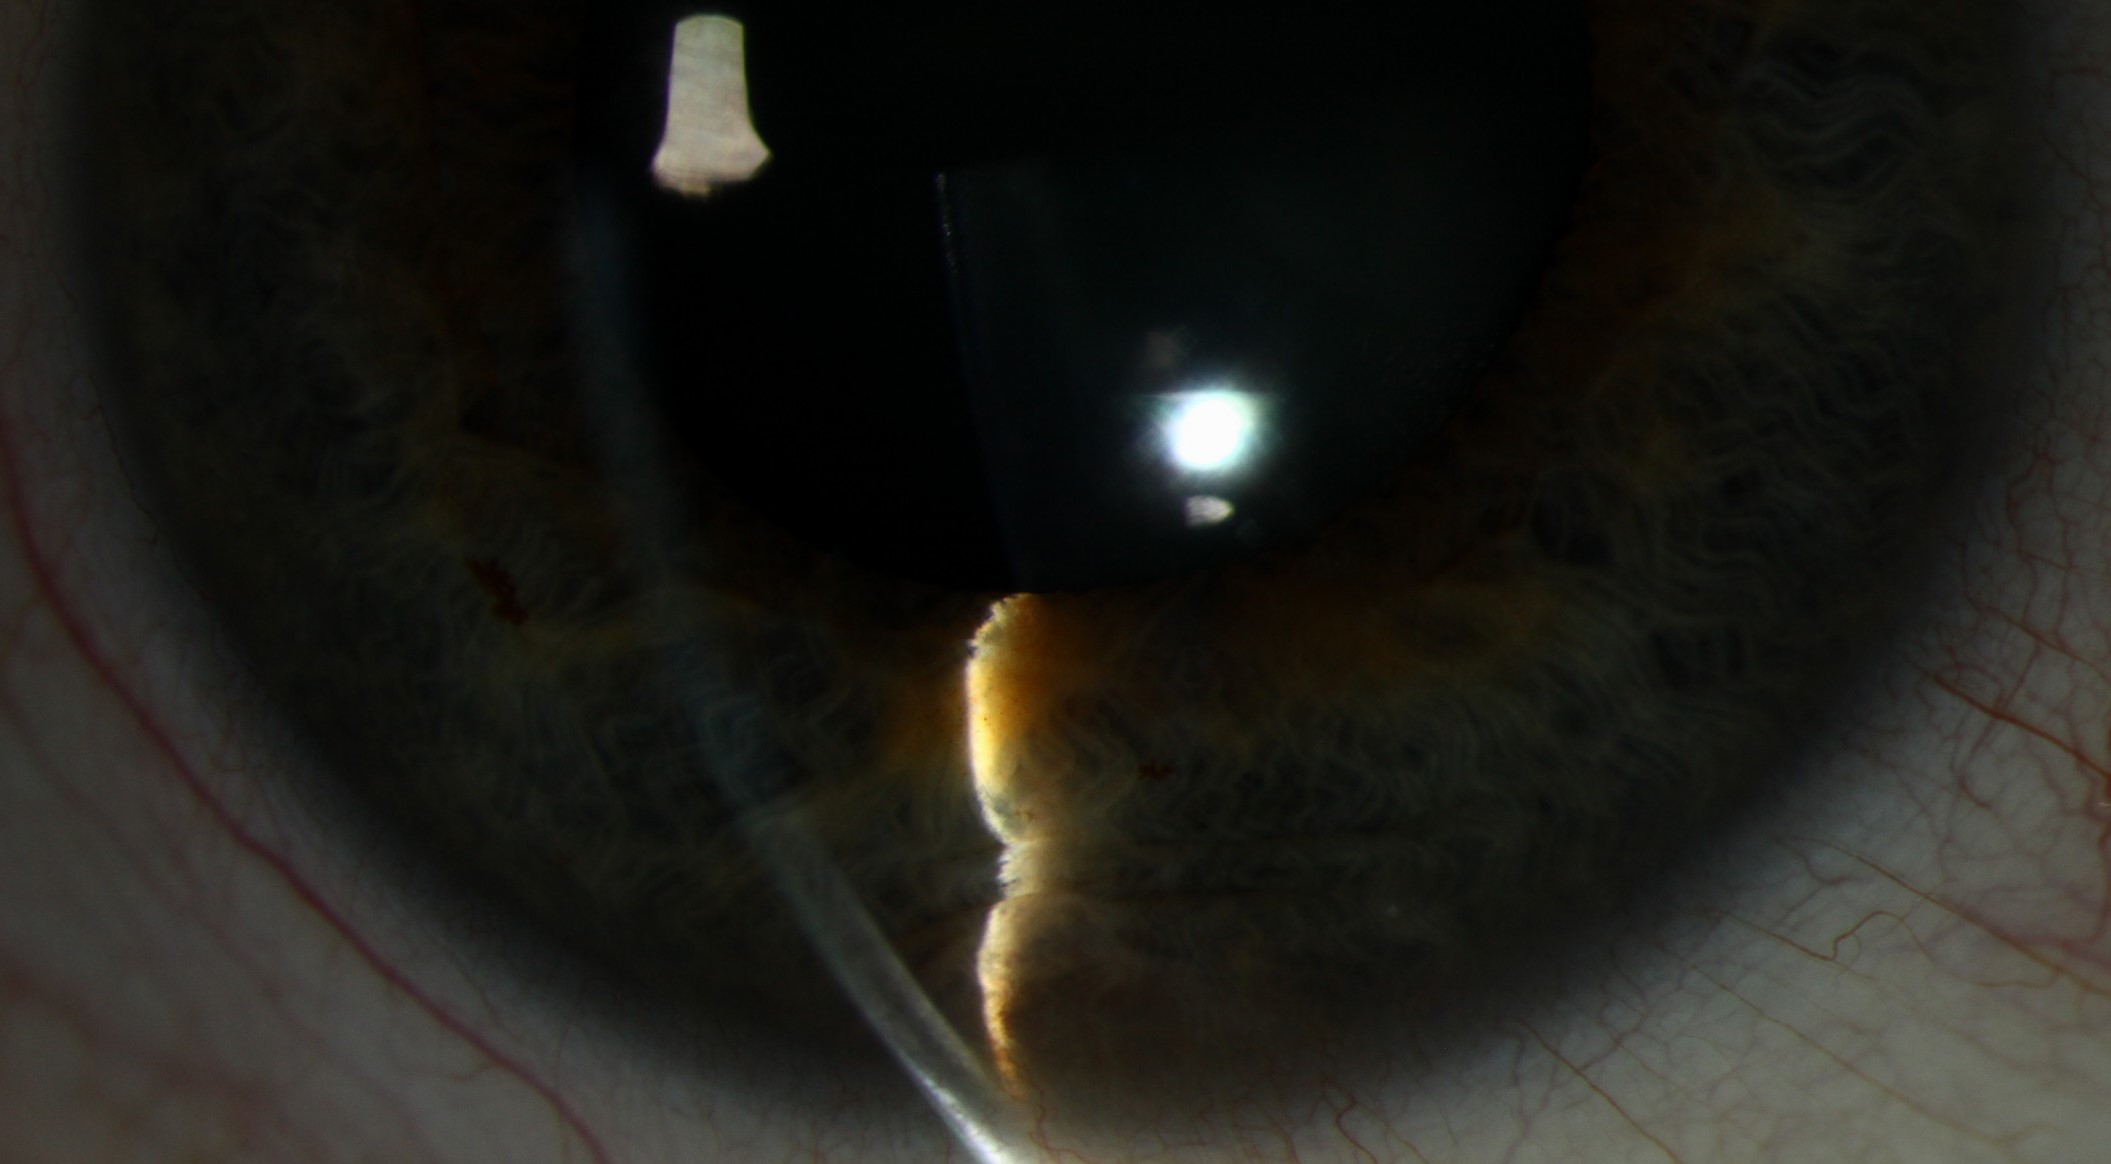
Management
Observation as the Default
Given the generally benign, stable natural history of iris pigment epithelial cysts, observation is the appropriate management for the great majority of these lesions, without the need for treatment or even particularly frequent follow-up once the diagnosis is confidently established.
- Baseline photographic documentation at the time of initial discovery is useful, supporting easy comparison if any future change is ever suspected
- Given the typically stable course, follow-up intervals for a classically appearing, asymptomatic cyst can generally be extended, aligning with routine, age-appropriate eye care rather than frequent, dedicated monitoring visits
When to Reconsider
- Any documented growth, change in appearance, or new symptoms should prompt reassessment, including consideration of ultrasound biomicroscopy to reconfirm the cystic nature of the lesion and exclude an alternative or evolving process
- Cysts causing genuine mechanical visual symptoms or significant cosmetic concern can be considered for treatment, including aspiration or, less commonly, surgical excision, though this is needed only in a small minority of cases
Imaging and differential diagnosis
Ultrasound biomicroscopy shows a thin-walled, cystic structure with clear contents behind the iris, which distinguishes a cyst from a solid tumor such as a melanoma. Look for pupil displacement, iris bulge, and angle narrowing. Compare with earlier photographs, and repeat imaging at an interval if there is doubt.
What to tell patients
Most cysts are stable and harmless, and they need no treatment. Treatment is considered if the cyst blocks the pupil or the angle, causes glaucoma, or obstructs vision. Laser cystotomy and aspiration are options, but they carry a risk of recurrence and inflammation, so observation is usually preferred.
Prognosis
Iris pigment epithelial cysts carry an excellent prognosis, with the great majority remaining entirely stable and asymptomatic indefinitely, and understanding this reliably benign natural history supports efficient, appropriately reassuring management once the diagnosis is confirmed.
Correctly recognizing this specific, common cyst type, and the characteristic locations and appearance it typically presents with, prevents unnecessary anxiety, over-testing, and over-monitoring for what is, in the overwhelming majority of cases, one of the more straightforwardly benign findings encountered in routine iris examination.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Shields JA, Kline MW, Augsburger JJ. Primary iris cysts: a review of the literature and report of 62 cases. Br J Ophthalmol. 1984;68:152-166.
- Shields JA, Shields CL, Lois N, Mercado G. Iris cysts in children: classification, incidence, and management. Br J Ophthalmol. 1999;83:334-338.
- Marigo FA, Esaki K, Finger PT, et al. Differential diagnosis of anterior segment cysts and tumors by ultrasound biomicroscopy in 100 consecutive cases. Ophthalmology. 1999;106:2131-2135.
- Behrouzi Z, Khodadoust A. Epithelial iris cyst treatment with double freeze-thaw cryotherapy. Ophthalmology. 2003;110:1885-1889.
Test yourself
A few questions straight from this article.
-
Iris pigment epithelial cysts arise from which structure?
These cysts originate from the posterior pigment epithelial layer, the deeply pigmented layer lining the back surface of the iris. -
Which type of iris cyst is the most frequently encountered in routine clinical practice?
Iris pigment epithelial cysts are by a wide margin the most commonly seen iris cyst, and most clinical effort goes into confirming a lesion fits this reliably benign pattern. -
Which simple bedside technique best confirms that a pigmented iris lesion is a cyst?
Light passes readily through a fluid-filled cyst and appears as a bright translucent glow, in clear contrast to the shadow cast by a solid lesion. -
On ultrasound biomicroscopy, which appearance separates an iris pigment epithelial cyst from a melanoma?
Ultrasound biomicroscopy shows a thin-walled cystic structure with clear contents behind the iris, which distinguishes a cyst from a solid tumour such as melanoma. -
What is the typical behaviour of an iris pigment epithelial cyst over long-term follow-up?
Stability in size over long-term follow-up is one of the most reassuring and clinically useful features of this cyst type. -
How are iris pigment epithelial cysts most often discovered?
They are typically incidental findings, and pupillary dilation often reveals a cyst that was not apparent with the pupil in its normal constricted state. -
What is the appropriate management for the great majority of iris pigment epithelial cysts?
Their benign, stable natural history makes observation appropriate, with baseline photographs taken at discovery to allow easy comparison if change is ever suspected. -
Why is observation usually preferred over laser cystotomy or aspiration for an iris pigment epithelial cyst?
Laser cystotomy and aspiration are available options, but because they carry a risk of recurrence and inflammation, observation is usually the preferred course. -
Where are peripheral iridociliary pigment epithelial cysts located?
Peripheral cysts sit near the iris root and can extend into or associate closely with the ciliary body region, overlapping with ciliary body cysts. -
Which finding should prompt reassessment of a previously stable iris pigment epithelial cyst?
Documented growth, altered appearance or new symptoms warrants reassessment, including ultrasound biomicroscopy to reconfirm the cystic nature and exclude an evolving process.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.