Posterior embryotoxon describes a prominent, anteriorly displaced Schwalbe line visible as a thin, gray-white ring near the corneal periphery, and while it is most often nothing more than a benign anatomic variant present in a meaningful minority of the general population, its presence, especially when combined with other subtle anterior segment findings, is specific enough to also serve as a recognized marker for Axenfeld-Rieger syndrome, making the context in which it is found the key to its interpretation.
What Schwalbe’s Line Normally Is
Schwalbe’s line marks the termination of Descemet membrane and the peripheral edge of the corneal endothelium at the anterior chamber angle, normally positioned at or very near the limbus and not typically visible as a distinct feature on routine slit-lamp examination without gonioscopy.
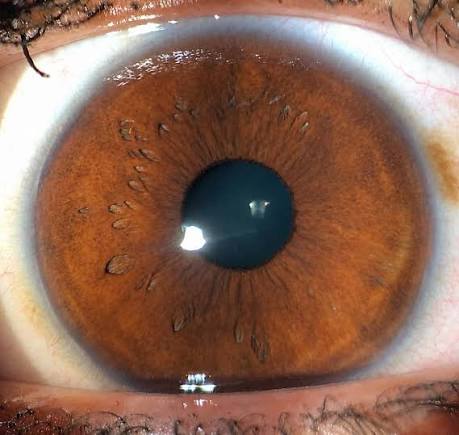
In posterior embryotoxon, this line is both more prominent (thickened) and displaced anteriorly, making it visible as a subtle, thin, circumferential or partial ring within the peripheral cornea, sometimes visible on careful slit-lamp examination alone, and always identifiable on gonioscopy.
Prevalence as an Isolated Finding
Posterior embryotoxon is a relatively common finding in the general population, present as an isolated, benign anatomic variant in a meaningful percentage of otherwise entirely normal eyes, without any associated visual, structural, or systemic significance in the great majority of these cases.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteAssociation With Axenfeld-Rieger Syndrome
Axenfeld-Rieger syndrome is a spectrum of anterior segment developmental disorders, and posterior embryotoxon is a recognized, though not universally present, component finding within this spectrum, becoming diagnostically significant specifically when it occurs alongside other characteristic findings of the syndrome rather than in isolation.
- Iris strands or adhesions extending from the peripheral iris to the prominent Schwalbe line (a finding termed Axenfeld anomaly when present together with posterior embryotoxon)
- Corectopia (displaced pupil) and iris stromal hypoplasia, seen in more involved cases (Rieger anomaly)
- Glaucoma develops in a substantial proportion of patients with the fuller Axenfeld-Rieger syndrome, related to associated angle developmental abnormality, and requires lifelong surveillance once the syndrome is identified
- Systemic associations in Rieger syndrome (when systemic features accompany the ocular findings) can include dental abnormalities, redundant periumbilical skin, and other developmental features
Clinical Evaluation
- Slit-lamp examination, ideally with retroillumination or careful direct observation, to identify the prominent, anteriorly displaced ring
- Gonioscopy is the definitive way to confirm posterior embryotoxon and to assess for associated iris strands or angle abnormalities that would support a diagnosis within the Axenfeld-Rieger spectrum rather than an isolated benign finding
- Careful assessment of iris architecture, pupil shape, and intraocular pressure when posterior embryotoxon is identified, since these findings, in combination, are what distinguish syndromic from isolated disease
- A systemic and family history and examination when features suggestive of the fuller Axenfeld-Rieger syndrome are present, given the autosomal dominant inheritance pattern recognized in a subset of affected families
Distinguishing Isolated From Syndromic Posterior Embryotoxon
The single most important clinical task when posterior embryotoxon is identified is determining whether it is an isolated finding or occurs alongside the other anterior segment features that would support a diagnosis within the Axenfeld-Rieger spectrum, since this distinction directly determines whether ongoing glaucoma surveillance and systemic evaluation are warranted.
Management
Isolated Posterior Embryotoxon
When posterior embryotoxon occurs in isolation, without any associated iris, pupil, or angle abnormality, no specific treatment or monitoring beyond routine, age-appropriate eye care is needed, since this represents a benign anatomic variant without independent clinical significance.
Axenfeld-Rieger Syndrome
When posterior embryotoxon occurs as part of the fuller Axenfeld-Rieger syndrome, ongoing glaucoma surveillance is essential given the substantial associated risk, including regular intraocular pressure monitoring and optic nerve assessment, with standard glaucoma treatment approaches applied if elevated pressure or optic nerve damage develops.
A systemic evaluation and, when appropriate, genetic counseling and family screening are appropriate given the recognized inheritance pattern in a subset of cases.
Prognosis
Isolated posterior embryotoxon carries an excellent prognosis with no expected impact on vision or ocular health throughout a patient’s life.
When identified as part of Axenfeld-Rieger syndrome, prognosis depends primarily on whether associated glaucoma develops and how effectively it is controlled, reinforcing why correctly placing this specific gonioscopic finding into its appropriate clinical context, isolated variant versus syndromic marker, is the central task each time it is encountered.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Shields MB. Axenfeld-Rieger syndrome: a theory of mechanism and distinctions from the iridocorneal endothelial syndrome. Trans Am Ophthalmol Soc. 1983;81:736-784.
- Alward WL. Axenfeld-Rieger syndrome in the age of molecular genetics. Am J Ophthalmol. 2000;130:107-115.
- Ozeki H, Shirai S, Ikeda K, Ogura Y. Anomalies associated with Axenfeld-Rieger syndrome. Graefes Arch Clin Exp Ophthalmol. 1999;237:730-734.
- Chang TC, Summers CG, Schimmenti LA, Grajewski AL. Axenfeld-Rieger syndrome: new perspectives. Br J Ophthalmol. 2012;96:318-322.
Test yourself
A few questions straight from this article.
-
How is Schwalbe line altered in posterior embryotoxon?
In posterior embryotoxon the line is both more prominent, meaning thickened, and displaced anteriorly so it becomes visible within the peripheral cornea. -
What does Schwalbe line normally mark at the anterior chamber angle?
Schwalbe line marks where Descemet membrane ends and the peripheral edge of the corneal endothelium sits, normally at or very near the limbus. -
How does posterior embryotoxon appear on slit-lamp examination?
The anteriorly displaced line shows as a subtle, thin, gray-white circumferential or partial ring within the peripheral cornea. -
Which examination definitively confirms posterior embryotoxon?
Gonioscopy is the definitive way to confirm posterior embryotoxon and to look for associated iris strands or angle abnormalities. -
Posterior embryotoxon is a recognized marker for which developmental disorder spectrum?
Posterior embryotoxon is a recognized though not universal component of the Axenfeld-Rieger spectrum of anterior segment developmental disorders. -
What additional finding alongside posterior embryotoxon defines Axenfeld anomaly?
Axenfeld anomaly is the term used when iris strands or adhesions run from the peripheral iris to the prominent Schwalbe line together with posterior embryotoxon. -
Which iris findings characterise Rieger anomaly in the Axenfeld-Rieger spectrum?
More involved cases, termed Rieger anomaly, show a displaced pupil (corectopia) together with iris stromal hypoplasia. -
Which systemic features can accompany the ocular findings in Rieger syndrome?
When systemic features accompany the ocular findings, dental abnormalities and redundant periumbilical skin are among the recognized associations. -
What follow-up does truly isolated posterior embryotoxon require?
With no associated iris, pupil or angle abnormality, posterior embryotoxon is a benign variant needing no specific treatment or extra monitoring. -
What chiefly determines prognosis when posterior embryotoxon forms part of Axenfeld-Rieger syndrome?
Within the syndrome, outcome depends primarily on development of associated glaucoma and the effectiveness of its control, which is why lifelong surveillance is needed.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.