Ciliary body melanoma is a form of uveal melanoma arising from the ciliary body, and its location, tucked behind the iris and largely hidden from direct view on routine examination, means it is often diagnosed later and at a larger size than choroidal melanoma, since the tumor can grow substantially before producing symptoms or becoming visible without specifically dilated, gonioscopic, or ultrasound examination directed at this region.
Why Ciliary Body Melanoma Is Often Diagnosed Late
The ciliary body sits behind the iris, outside the field of view during a standard undilated examination, and even with pupillary dilation, a tumor confined mostly to the ciliary body can remain difficult to see directly unless specifically sought with techniques such as scleral depression, gonioscopy, or ultrasound biomicroscopy.
This anatomic concealment is the central reason ciliary body melanomas tend to present at a larger size than their choroidal counterparts, since the tumor often grows silently until it produces a secondary sign, such as visible extension beyond the ciliary body, lens subluxation, or a sentinel episcleral vessel, that finally draws attention to it.
Clinical Clues
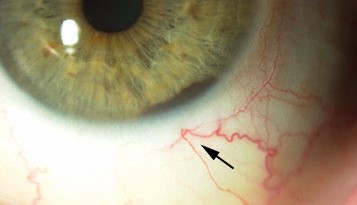
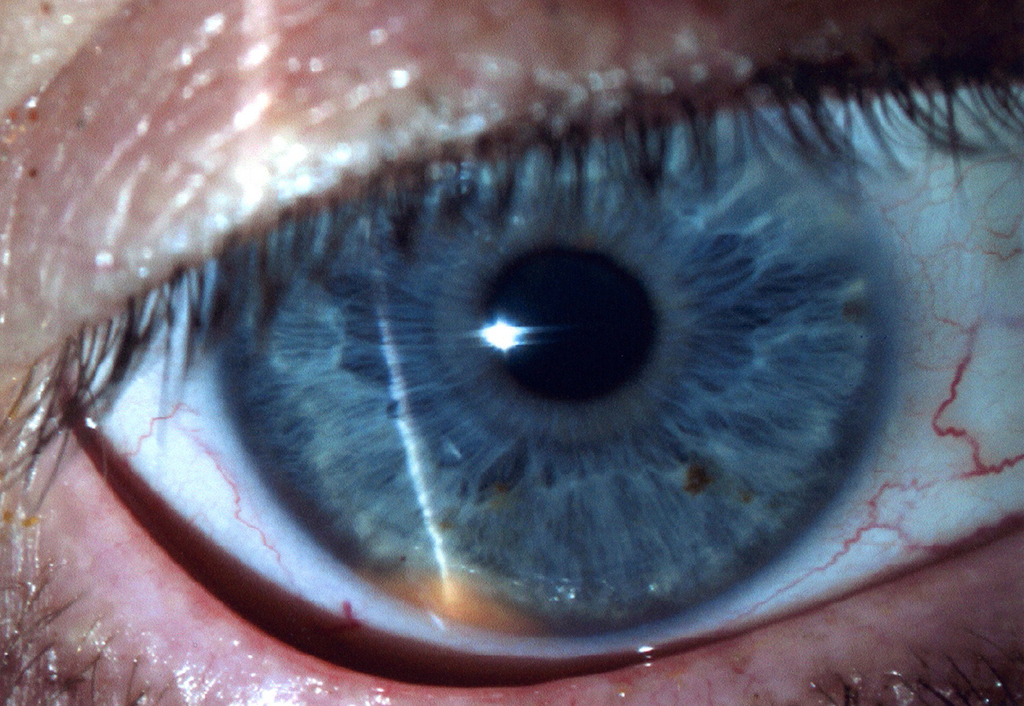
- A sentinel (dilated, tortuous) episcleral vessel in a localized area, sometimes the first visible external sign pointing toward an underlying ciliary body tumor
- Unexplained, often sector-limited, lens subluxation or cataract, from local zonular disruption caused by the adjacent tumor
- Asymmetric or unexplained elevation of intraocular pressure, sometimes from tumor-related angle involvement
- A visible mass extending into the anterior chamber angle on gonioscopy, or pigment dispersion in the angle, in more advanced cases
- Blurred vision from tumor-induced astigmatism, cataract, or, in larger tumors, secondary retinal effects
- In some cases, the tumor is found incidentally on a dilated examination performed for an unrelated reason
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteDiagnostic Evaluation
- Careful examination with maximal pupillary dilation, scleral depression, and gonioscopy to directly visualize as much of the ciliary body and angle as possible
- Ultrasound biomicroscopy, a high-frequency ultrasound technique specifically suited to imaging the anterior segment structures, including the ciliary body, in detail not achievable with standard B-scan ultrasound alone
- Standard B-scan ultrasound, useful for characterizing tumor size, extent, and internal reflectivity, and for assessing posterior extension
- Transillumination, which can sometimes help outline the tumor’s extent by demonstrating a shadow where the pigmented mass blocks transmitted light
- Fine-needle aspiration biopsy, considered in select cases for diagnostic confirmation or for prognostic genetic testing, following the same general principles applied to uveal melanoma more broadly
Management
Plaque Brachytherapy
For appropriately sized tumors, plaque brachytherapy, a form of localized radiation treatment, can be used to treat ciliary body melanoma while preserving the eye, similar in principle to its use for choroidal melanoma, though the anterior location can pose specific technical challenges for plaque placement (see choroidal melanoma treatment).
Local Resection
Surgical local resection of the tumor, removing the ciliary body mass while preserving the remainder of the eye, is an option in some cases, particularly for tumors not ideally suited to radiation treatment, though it carries its own technical challenges and risks, including vitreous hemorrhage and cataract.
Enucleation
For very large tumors, or those with extensive local invasion or other features unfavorable for eye-preserving treatment, enucleation remains an appropriate and sometimes necessary option, following the same general principles used in managing advanced choroidal melanoma.
Prognostic Considerations
Ciliary body melanoma has traditionally been associated with a somewhat worse prognosis compared with choroidal melanoma of comparable size, related in part to its tendency toward later diagnosis at a larger tumor size and, in some studies, to a possibly higher intrinsic rate of unfavorable genetic and histologic features, underscoring the importance of prompt, specifically directed examination when any of the clinical clues above are present.
Systemic Surveillance
As with other forms of uveal melanoma, patients diagnosed with ciliary body melanoma require systemic surveillance for metastatic disease, most commonly to the liver, with the surveillance interval and intensity often informed by tumor size and, when available, prognostic genetic testing results.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Shields CL, Shields JA, Gross NE, Schwartz GP, Lally SE. Survey of 520 eyes with uveal metastases. Ophthalmology. 1997;104:1265-1276.
- Shields CL, Furuta M, Berman EL, et al. Choroidal nevus transformation into melanoma: analysis of 2514 consecutive cases. Arch Ophthalmol. 2009;127:981-987.
- Marigo FA, Finger PT. Anterior segment tumors: current concepts and innovative techniques. Surv Ophthalmol. 2003;48:569-593.
- Char DH. Uveal melanoma: diagnosis, treatment and management. Curr Opin Ophthalmol. 1997;8:29-32.
Test yourself
A few questions straight from this article.
-
Why is ciliary body melanoma typically diagnosed later and at a larger size than choroidal melanoma?
The ciliary body sits behind the iris, outside the view of a standard examination, so a tumour there can grow silently unless specifically sought with scleral depression, gonioscopy or ultrasound biomicroscopy. -
A localised dilated, tortuous episcleral vessel in one quadrant should raise suspicion of which intraocular tumour?
A sentinel dilated, tortuous episcleral vessel over a localised area is sometimes the first visible external sign of an underlying ciliary body tumour. -
Sector lens subluxation beside a ciliary body melanoma arises through which mechanism?
Unexplained, often sector-limited lens subluxation or cataract results from local zonular disruption caused by the neighbouring ciliary body tumour. -
Which technique images the ciliary body in detail that standard B-scan ultrasound alone cannot achieve?
Ultrasound biomicroscopy is a high-frequency technique suited to the anterior segment, imaging the ciliary body in detail beyond what standard B-scan provides. -
On transillumination of a suspected ciliary body melanoma, which finding helps outline the tumour?
Transillumination can outline tumour extent by showing a shadow where the pigmented mass blocks transmitted light. -
In ciliary body melanoma, fine-needle aspiration biopsy is considered in selected cases for which purpose?
Fine-needle aspiration biopsy is used in select cases either to confirm the diagnosis or to obtain prognostic genetic testing, following general uveal melanoma principles. -
What technical difficulty does the anterior position of a ciliary body melanoma create in plaque brachytherapy?
Plaque brachytherapy can treat appropriately sized ciliary body melanoma while preserving the eye, but the anterior location poses specific technical challenges for plaque placement. -
Local surgical resection of a ciliary body melanoma carries which recognised risks?
Local resection preserves the rest of the eye and suits tumours less ideal for radiation, but brings technical challenges and risks including vitreous haemorrhage and cataract. -
How does the prognosis of ciliary body melanoma compare with choroidal melanoma of comparable size?
Ciliary body melanoma has traditionally carried a somewhat worse prognosis than choroidal melanoma of similar size, linked to later diagnosis at larger size and possibly more unfavourable genetic and histologic features. -
Systemic surveillance after ciliary body melanoma targets metastatic disease most commonly in which organ?
Like other uveal melanomas, ciliary body melanoma requires surveillance for metastasis, most commonly to the liver, with interval guided by tumour size and prognostic genetic results.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.