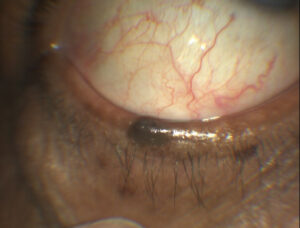
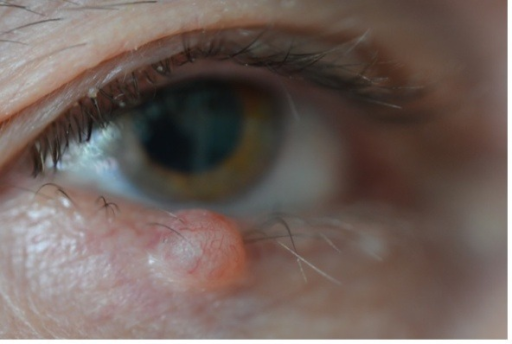
Eyelid margin tumors are most often basal cell carcinoma, with squamous cell carcinoma and sebaceous carcinoma making up most of the rest, and complete excision, usually by Mohs micrographic surgery, leaves a defect that must be reconstructed with attention to both eyelid function and cosmetic appearance.
The oculoplastic surgeon’s job begins where the Mohs surgeon’s ends, and the choice of reconstruction depends almost entirely on how much of the eyelid margin is missing.
Why Mohs Surgery Comes First
Mohs micrographic surgery examines the entire excision margin under the microscope in real time, layer by layer, which gives the highest confirmed clearance rate of any technique for periocular skin cancer while sparing as much normal tissue as possible.
This matters more at the eyelid than almost anywhere else on the body, since even a few extra millimeters of unnecessary excision can change which reconstruction option is available.
Assessing the Defect
The reconstructive plan depends on the size of the defect relative to the horizontal length of the eyelid, and on whether the defect is full-thickness or involves only skin and muscle.
- Small full-thickness defects, generally up to about a quarter of the eyelid length, can often be closed directly
- Moderate defects, up to about half the eyelid length, usually need a lateral canthotomy and cantholysis to gain enough laxity for direct closure
- Larger defects require flap or graft reconstruction, borrowing tissue from adjacent structures
The lower eyelid tolerates larger direct closures than the upper eyelid because of differences in eyelid mobility and the greater functional consequences of upper eyelid tightness.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteReconstruction Options by Defect Size
Direct Closure
A simple full-thickness closure in layers, with careful margin apposition, is used for small defects and gives the best cosmetic and functional result when tension is low.
Semicircular and Advancement Flaps
Techniques such as the Tenzel semicircular flap advance adjacent lid and lateral canthal tissue to close moderate defects without needing a separate posterior lamella reconstruction.
Tarsoconjunctival Flaps
The Hughes procedure, using a tarsoconjunctival flap from the upper eyelid to reconstruct the posterior lamella of a large lower eyelid defect, combined with an anterior lamellar skin graft or flap, is a workhorse technique for large lower lid defects, performed in two stages with division of the flap several weeks after the initial reconstruction.
Cutler-Beard and Other Upper Eyelid Techniques
Large upper eyelid defects, which are less common but more functionally critical because of the risk to corneal protection, may need a full-thickness lower eyelid bridge flap or other specialized reconstruction.
Functional Priorities
Reconstruction aims to restore a stable eyelid margin, adequate closure to protect the cornea, and normal eyelid position without entropion, ectropion, or lagophthalmos.
Tumor clearance always comes first, and reconstruction should never be planned in a way that compromises the oncologic margin or delays confirmation of clear margins.
Follow-Up
Patients need long-term monitoring for tumor recurrence, particularly with basal cell carcinoma subtypes prone to recurrence and with sebaceous carcinoma, which can recur or spread despite apparently clear margins (see sebaceous gland carcinoma).
Eyelid function, tear film, and corneal health are also monitored after reconstruction, since even a well-executed repair can develop late contracture or malposition.
Prognosis
Most patients achieve good functional and cosmetic outcomes when tumor excision and reconstruction are properly staged and matched to defect size.
The combination of Mohs surgery for tumor clearance and a reconstruction chosen to match the specific defect gives both the best chance of cure and the best chance of a normal-looking, well-functioning eyelid.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Malhotra R, Huilgol SC, Huynh NT, Selva D. The Australian Mohs database, part II: periocular basal cell carcinoma outcome at 5-year follow-up. Ophthalmology. 2004;111:631-636.
- Hughes WL. A new method for rebuilding a lower lid. Arch Ophthalmol. 1937;17:1008-1017.
- Tenzel RR, Stewart WB. Eyelid reconstruction by the semicircle flap technique. Ophthalmology. 1978;85:1164-1169.
- Mohs FE. Chemosurgery: a microscopically controlled method of cancer excision. Arch Surg. 1941;42:279-295.
Test yourself
A few questions straight from this article.
-
Which malignancy accounts for most eyelid margin tumors?
Basal cell carcinoma is the commonest eyelid margin tumor, with squamous cell carcinoma and sebaceous carcinoma making up most of the remainder. -
What makes Mohs micrographic surgery the preferred excision for periocular skin cancer?
Mohs examines the entire excision margin under the microscope layer by layer in real time, giving the highest confirmed clearance rate while sparing normal tissue. -
Up to roughly what share of eyelid length can a full-thickness defect usually be closed directly?
Small full-thickness defects, generally up to about a quarter of the horizontal eyelid length, can often be closed directly in layers. -
Which manoeuvre gains laxity for direct closure of a defect up to half the eyelid length?
Moderate defects of up to about half the eyelid length usually require lateral canthotomy and cantholysis to release enough laxity for direct closure. -
What does the Tenzel semicircular flap achieve in eyelid margin reconstruction?
The Tenzel semicircular flap advances adjacent lid and lateral canthal tissue to close moderate defects without a separate posterior lamella reconstruction. -
What tissue does the Hughes procedure use to rebuild the posterior lamella of a large lower lid defect?
The Hughes procedure brings a tarsoconjunctival flap down from the upper eyelid for the posterior lamella, paired with an anterior lamellar skin graft or flap. -
How is a Hughes tarsoconjunctival flap reconstruction staged?
The Hughes flap is a two-stage technique, with division of the flap performed several weeks after the initial reconstruction. -
Which eyelid tolerates larger direct closures after tumor excision?
The lower eyelid tolerates larger direct closures because of differences in lid mobility and the greater functional cost of upper eyelid tightness. -
Which eyelid malignancy can recur or spread despite apparently clear excision margins?
Long-term surveillance is needed because sebaceous carcinoma can recur or spread even when margins appear clear, as can recurrence-prone basal cell subtypes. -
Which principle governs planning of eyelid reconstruction after tumor excision?
Tumor clearance always takes priority, and no reconstructive plan should compromise the oncologic margin or delay confirmation that margins are clear.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.