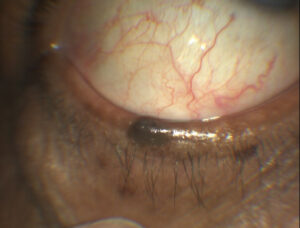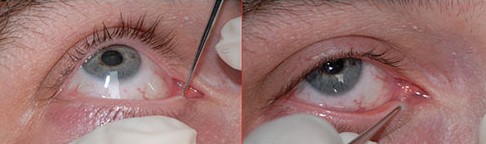
Canalicular laceration repair restores the drainage pathway that carries tears from the eyelid margin into the nose after an eyelid injury that cuts across the canaliculus, and it is one of the few oculoplastic repairs where the timing and the first surgeon’s technique largely determine whether the patient ends up with normal tearing or a lifetime of epiphora.
Missing or poorly repairing the canaliculus is far harder to fix later than getting it right at the first operation.
Anatomy at Risk
Tears drain through the punctum into the canaliculus, which runs medially from each eyelid to join the common canaliculus before entering the lacrimal sac.
Any laceration medial to the punctum, on either the upper or lower eyelid, risks transecting the canaliculus, and lacerations near the medial canthus should be assumed to involve the canalicular system until proven otherwise.
Common Mechanisms
- Blunt trauma with eyelid avulsion, often from a fall or assault
- Dog bites, which frequently involve the medial eyelid and can cause complex, ragged canalicular injuries
- Sharp lacerations from glass, metal, or other objects
- Motor vehicle accidents with facial trauma
A medial eyelid laceration in any of these settings should prompt careful examination for canalicular involvement before the wound is closed.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteExamination
- Identify both cut ends of the canaliculus under magnification, which can be difficult in a swollen, bleeding, or fatty periorbital wound
- Probe the punctum and canaliculus gently to help trace the proximal cut end
- Irrigate through the uninvolved punctum to see fluid or air bubble through the wound, confirming the location of the distal cut end
- Assess for associated injuries, including the medial canthal tendon, orbital septum, and globe
A thorough search for the cut ends, even in a difficult wound, is worth the time, since a missed canalicular laceration heals with a scarred, nonfunctional drainage system.
Timing of Repair
Repair is ideally performed within 24 to 48 hours of injury, before the wound edges retract and become more difficult to identify and appose.
Delayed repair is still attempted when necessary, but the cut ends become harder to find and the surgical result is generally less predictable the longer repair is postponed.
Surgical Technique
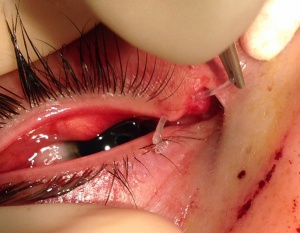
Stenting
A silicone stent is passed through the canalicular system to keep the lumen open while it heals, either as a monocanalicular stent confined to the injured canaliculus, or as a bicanalicular stent that passes through both puncta and into the nose, anchored there.
The stent is left in place for weeks to months, allowing the canalicular epithelium to heal around a patent lumen rather than scarring closed.
Suture Repair
The canalicular wall and surrounding tissue are reapposed with fine sutures over the stent, followed by layered closure of the orbicularis muscle and skin.
Careful realignment of the medial canthal anatomy is part of the repair when the medial canthal tendon is also involved.
Stent Removal
Stents are typically removed after a period of weeks to a few months, once the surgeon judges the canalicular epithelium has healed with an adequate lumen.
Complications
- Stent-related irritation, corneal abrasion from a displaced stent, or premature stent loss
- Canalicular stenosis or obstruction despite repair, leading to chronic epiphora
- Punctal or canthal malposition if the surrounding tissue is not properly realigned
- Missed or incompletely repaired lacerations, which usually result in permanent obstruction of that canaliculus
Prognosis
Most repaired canaliculi regain functional patency, particularly when repair is performed promptly by a surgeon experienced in identifying and stenting the cut ends.
Even when one canaliculus fails to regain full function, the fellow canaliculus on the same eyelid, or the uninjured eyelid’s canaliculus, often provides enough drainage to prevent troublesome epiphora, though bicanalicular injury carries a higher risk of persistent symptoms.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Jordan DR, Gilberg S, Mawn LA. The round-tip Crawford probe: a small change that makes a big difference. Ophthalmic Plast Reconstr Surg. 2008;24:170-171.
- Wulc AE, Arterberry JF. The pathogenesis of canalicular laceration. Ophthalmology. 1991;98:1243-1249.
- Naik MN, Kelapure A, Rath S, Honavar SG. Management of canalicular lacerations: epidemiological aspects and experience with Mini-Monoka monocanalicular stent. Am J Ophthalmol. 2008;145:375-380.
- Kennedy RH, May J, Dailey J, Flanagan JC. Canalicular laceration: an 11-year epidemiologic and clinical study. Ophthalmic Plast Reconstr Surg. 1990;6:46-53.
Test yourself
A few questions straight from this article.
-
Which eyelid laceration should be assumed to involve the canalicular system?
A laceration medial to the punctum on either eyelid risks transecting the canaliculus, and injuries near the medial canthus are assumed canalicular until proven otherwise. -
Within what interval is canalicular laceration repair ideally performed?
Repair is ideally carried out within 24 to 48 hours of injury, before the cut edges retract and become harder to find and appose. -
Why does delaying canalicular repair worsen the surgical result?
With delay the cut ends retract and become more difficult to identify and bring together, making the outcome of repair less predictable. -
Which manoeuvre helps locate the distal cut end of a lacerated canaliculus?
Irrigating through the uninvolved punctum makes fluid or an air bubble appear in the wound, confirming where the distal cut end lies. -
What is the purpose of a silicone stent in canalicular laceration repair?
The stent keeps the canalicular lumen patent so the epithelium heals around an open channel instead of scarring closed. -
How does a bicanalicular stent differ from a monocanalicular one?
A monocanalicular stent stays within the injured canaliculus, whereas a bicanalicular stent passes through both puncta and into the nose, where it is anchored. -
When is a canalicular stent typically removed after repair?
Stents stay in for weeks to a few months and are removed once the surgeon judges the canalicular epithelium has healed with an adequate lumen. -
Which injury mechanism characteristically causes ragged, complex medial eyelid canalicular wounds?
Dog bites frequently involve the medial eyelid and tend to produce complex, ragged canalicular injuries. -
What is the usual consequence of a canalicular laceration that is missed at the first repair?
A missed or incompletely repaired laceration heals as a scarred, nonfunctional channel and usually leaves that canaliculus permanently obstructed. -
Which associated structures should be assessed in a medial eyelid laceration?
Examination includes a search for associated injury to the medial canthal tendon, the orbital septum and the globe itself.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.