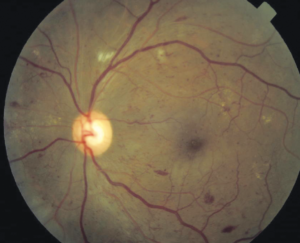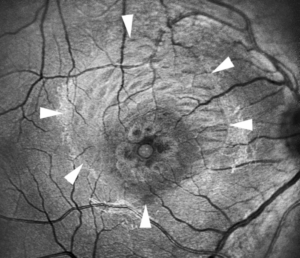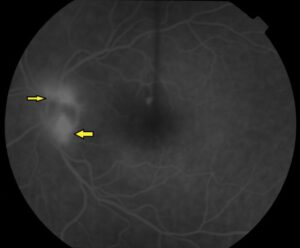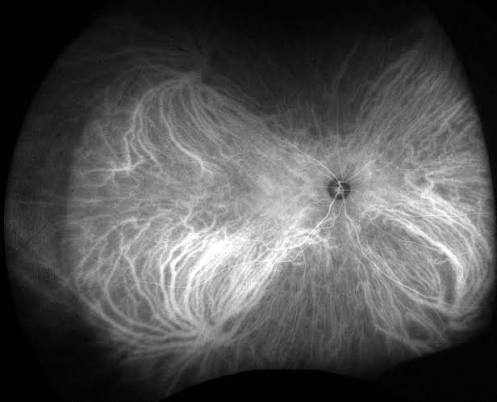
Indocyanine green angiography, or ICG angiography, images the choroidal circulation using a dye that behaves very differently from fluorescein, making it the preferred imaging tool whenever the choroid itself, rather than the retina, is the structure under investigation.
Fluorescein angiography, the more familiar and widely used dye study, is excellent for retinal vasculature but performs poorly at visualizing the choroid, since fluorescein binds extensively to plasma proteins and leaks readily from the naturally fenestrated choriocapillaris, obscuring the detail ICG can reveal.
Understanding why ICG behaves so differently from fluorescein is the key to understanding when it actually adds diagnostic value beyond what a standard fluorescein study already provides.
ICG angiography is used more selectively than fluorescein overall, reserved for the specific subset of cases where choroidal pathology is suspected rather than as a routine first-line retinal imaging study.
Why ICG Sees the Choroid Better
Indocyanine green is a larger molecule that binds almost completely to plasma proteins, which limits its leakage through the naturally fenestrated choriocapillaris in a way that free fluorescein cannot match.
ICG also fluoresces in the near-infrared spectrum, a wavelength that penetrates the retinal pigment epithelium, blood, and pigment more effectively than the visible-light wavelength fluorescein uses, allowing better visualization of structures deep to the RPE.
Together, reduced leakage and better tissue penetration are what make ICG the superior choice specifically for visualizing choroidal vasculature and lesions that fluorescein angiography images poorly or not at all.
Optical coherence tomography has taken over some of ICG’s traditional diagnostic territory in recent years, but ICG retains a distinct, complementary role, particularly for characterizing dynamic vascular filling patterns that a static OCT scan cannot capture.
Indications
- Polypoidal choroidal vasculopathy, where ICG is essential for visualizing the characteristic polypoidal choroidal lesions that define the diagnosis and are difficult to appreciate on fluorescein alone
- Central serous chorioretinopathy, discussed in its own dedicated article on this site, where ICG can reveal areas of choroidal vascular hyperpermeability contributing to the disease
- Choroidal tumors, including choroidal melanoma and hemangioma, both discussed in their own dedicated articles on this site, where ICG helps characterize the tumor’s vascular pattern
- Inflammatory choroidal disease, including birdshot chorioretinopathy and other white dot syndromes with a significant choroidal component, where ICG can reveal hypofluorescent inflammatory foci not visible on fluorescein or clinical exam
- Occult choroidal neovascularization, where ICG’s better penetration can sometimes localize a neovascular lesion that fluorescein leakage alone obscures
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteInterpreting the Study
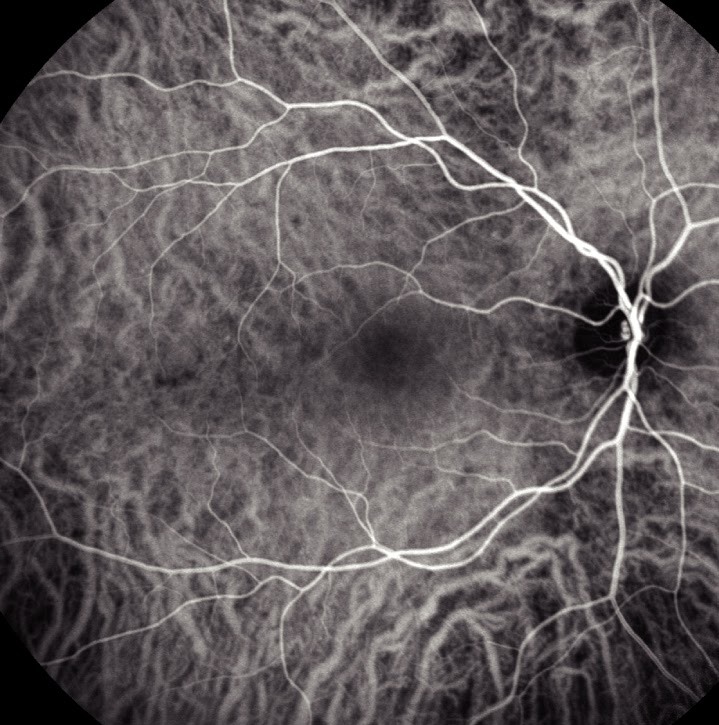
Early-phase ICG images show the large choroidal vessels filling before the finer choriocapillaris becomes visible, a pattern distinct from the arterial-then-venous retinal filling sequence seen on fluorescein.
Mid- and late-phase imaging is where much of the diagnostic value lies, revealing patterns of hyperfluorescence or hypofluorescence corresponding to abnormal vessels, inflammatory foci, or tumor vasculature that would otherwise remain hidden beneath the RPE on standard exam and fluorescein imaging.
Interpretation benefits from correlation with simultaneous or near-simultaneous fluorescein angiography in many cases, since the two dyes provide complementary rather than fully overlapping information about the same eye.
Recognizing normal variants and common artifacts on ICG imaging takes deliberate experience, much like interpreting any angiographic study, and unfamiliarity with the normal choroidal filling pattern can lead to overcalling subtle findings as pathologic.
Practical Considerations
ICG carries its own allergy profile, distinct from fluorescein, and specific caution is needed in patients with iodine or shellfish allergy given the iodide component in the ICG formulation, though the clinical significance of this cross-reactivity has been debated.
The procedure itself is performed similarly to fluorescein angiography, with dye injected intravenously and sequential images captured over time using a camera system capable of detecting the near-infrared fluorescence.
Combined fluorescein and ICG angiography, performed in the same sitting, is common practice in centers regularly managing choroidal disease, since the complementary information from both dyes together often exceeds what either study provides alone.
Access to ICG angiography is less universal than fluorescein, since it requires specific camera capability and dye stock not every practice maintains, which is a practical factor in deciding when referral to a center with this capability is warranted.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Yannuzzi LA. Indocyanine green angiography: a perspective on use in the clinical setting. American Journal of Ophthalmology.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 12: Retina and Vitreous.
- Spaide RF, Koizumi H, Pozzoni MC. Enhanced depth imaging spectral-domain optical coherence tomography. American Journal of Ophthalmology.
Test yourself
A few questions straight from this article.
-
Indocyanine green angiography is the preferred dye study for imaging which structure?
ICG is chosen whenever the choroid rather than the retina is the structure in question, which is where fluorescein performs poorly. -
In which part of the spectrum does indocyanine green fluoresce?
ICG fluoresces in the near-infrared, and that wavelength is central to its ability to image structures lying deep to the retinal pigment epithelium. -
Why does ICG visualise structures deep to the retinal pigment epithelium so well?
Near-infrared light passes through the RPE, blood and pigment more effectively than the visible wavelength used for fluorescein imaging. -
Which property of indocyanine green limits its leakage from the choriocapillaris?
ICG is a larger molecule that binds almost completely to plasma proteins, so it does not escape through the naturally fenestrated choriocapillaris. -
For which condition is ICG angiography essential to establish the diagnosis?
The defining polypoidal choroidal lesions are hard to appreciate on fluorescein alone, so ICG is essential to demonstrate them. -
What does ICG angiography reveal in central serous chorioretinopathy?
ICG shows areas of choroidal vascular hyperpermeability that contribute to the disease process. -
In birdshot chorioretinopathy and related white dot syndromes, ICG characteristically shows what?
ICG uncovers hypofluorescent inflammatory foci that are not apparent on fluorescein angiography or on clinical examination. -
Early-phase ICG angiography images show which filling pattern?
The large choroidal vessels fill first and the finer choriocapillaris appears afterwards, unlike the arterial-then-venous retinal sequence on fluorescein. -
Which allergy history calls for particular caution before ICG angiography?
The ICG formulation contains an iodide component, so iodine or shellfish allergy warrants caution, although how clinically significant the cross-reactivity is remains debated. -
What distinct role does ICG angiography retain despite advances in OCT?
OCT has absorbed some of ICG's former territory, but a static scan cannot show the dynamic filling patterns that an angiogram captures over time.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.