Polyarteritis nodosa is a necrotizing vasculitis of medium-sized arteries.
It can involve the eye in a sizable share of patients.
Therefore, the ophthalmologist may be the first to see signs of the disease.
What Polyarteritis Nodosa Is
The Chapel Hill consensus defines it as necrotizing arteritis of medium or small arteries without glomerulonephritis.
It is not linked to antineutrophil cytoplasmic antibodies.
Also, it affects the skin, nerves, kidneys and gut.
As a result, it presents with varied systemic signs.
Causes of Polyarteritis Nodosa
Many cases are idiopathic.
Hepatitis B infection is a classic trigger.
Also, a monogenic form called deficiency of adenosine deaminase 2 mimics the disease in children.
Therefore, test for infection and genetics where relevant.
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteSystemic Features of Polyarteritis Nodosa
Patients have fever, weight loss and myalgia.
Livedo reticularis, nodules and mononeuritis multiplex are common.
Also, hypertension and renal infarcts occur.
In addition, abdominal pain can signal mesenteric ischemia.
How Often the Eye Is Involved
Akova and colleagues found ocular signs in a considerable share of patients with polyarteritis nodosa.
Rothschild and colleagues found ocular signs at diagnosis in a minority of patients with systemic necrotizing vasculitis.
Also, the eye may be the first site.
Therefore, ocular findings can lead the diagnosis.
Choroidal Vasculopathy
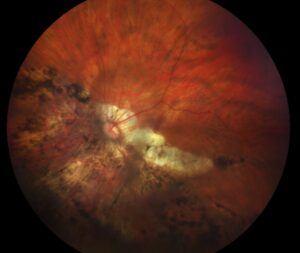
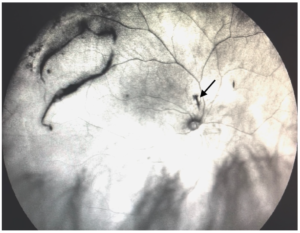
Occlusion of choroidal arteries causes patchy infarcts.
Fluorescein angiography shows delayed filling and hypofluorescent areas.
Also, serous detachment of the retina can follow.
As a result, patients may notice central blur.
Retinal Vasculitis
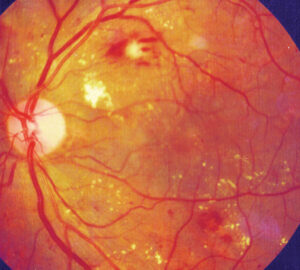
Retinal vessels show sheathing, hemorrhages and cotton-wool spots.
Branch occlusion can occur.
Also, neovascularization may follow ischemia (see retinal vasculitis).
Therefore, angiography is needed to map the damage.
Hypertensive Retinopathy and Choroidopathy
Renal involvement can cause severe hypertension.
The retina may show hypertensive changes with exudates and disc swelling.
Also, choroidal infarcts may mimic vasculitic lesions.
Therefore, check the blood pressure at every visit.
Anterior Segment and Orbit
Peripheral ulcerative keratitis and scleritis are well known in vasculitis.
Orbital inflammation and optic neuropathy occur less often.
Also, these signs signal active disease.
As a result, anterior findings should prompt a systemic review.
Differential Diagnosis
Giant cell arteritis causes ischemic optic neuropathy and choroidal ischemia in older patients.
Granulomatosis with polyangiitis shows scleritis and orbital disease.
Also, lupus and antiphospholipid syndrome produce similar fundus signs.
Therefore, serology and imaging help.
Diagnosing Polyarteritis Nodosa
Biopsy of an affected tissue or angiography of visceral vessels confirms the diagnosis.
Aneurysms in renal or mesenteric arteries are typical.
Also, blood tests show high inflammatory markers.
In addition, test for hepatitis B.
Ophthalmic Workup
Perform dilated examination, OCT and fluorescein angiography.
Indocyanine angiography shows choroidal involvement.
Also, check visual fields in optic nerve disease.
As a result, the eye work-up documents extent and activity.
Treatment of Polyarteritis Nodosa
High-dose steroids are the first step.
Cyclophosphamide is added for severe or organ-threatening disease.
Also, treat hepatitis B-related disease with antivirals and plasma exchange.
Therefore, treatment depends on the cause.
Treatment of Polyarteritis Nodosa of Ocular Disease
Systemic therapy usually controls the eye.
Laser or anti-VEGF drugs treat neovascularization and edema.
Also, steroid injections may help macular edema.
In addition, follow with angiography.
Prognosis of Polyarteritis Nodosa
Early treatment improves survival and organ outcomes.
Eye involvement signals severe disease.
Also, vision loss can be permanent after infarcts.
As a result, quick recognition matters.
Follow-Up
Monitor disease activity with symptoms, markers and imaging.
Relapses occur, especially after tapering.
Also, repeat eye examinations during follow-up.
Therefore, coordinate with the rheumatologist.
Pitfalls to Avoid
- Do not miss systemic disease behind an unexplained choroidopathy
- Never attribute all findings to hypertension
- Do not start steroids without a plan for the systemic workup
- Never forget to test for hepatitis B
Pediatric Disease and DADA2
Children with a PAN-like illness may have mutations in the ADA2 gene.
They show strokes, fever and skin changes.
Also, anti-TNF therapy helps.
Therefore, consider genetic testing in early-onset disease.
Imaging Pattern in Choroidal Infarcts
Indocyanine angiography shows hypofluorescent patches that match the lobular pattern.
Fluorescein shows early hypofluorescence and late staining.
Also, OCT shows serous fluid and thickening.
As a result, the pattern separates vasculitis from other choroidopathies.
Medication Monitoring
Cyclophosphamide and steroids need laboratory monitoring.
Watch for infection, bone loss and cataract.
Also, check eye pressure on steroids.
Therefore, eye and systemic reviews go together.
For the latest studies, see the PubMed results for polyarteritis nodosa.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Akova YA, Jabbur NS, Foster CS. Ocular presentation of polyarteritis nodosa: clinical course and management with steroid and cytotoxic therapy. Ophthalmology. 1993;100:1775-1781.
- Jennette JC, Falk RJ, Bacon PA, et al. 2012 revised International Chapel Hill Consensus Conference nomenclature of vasculitides. Arthritis Rheum. 2013;65:1-11.
- Pagnoux C, Seror R, Henegar C, et al. Clinical features and outcomes in 348 patients with polyarteritis nodosa: a systematic retrospective study of patients diagnosed between 1963 and 2005 and entered into the French Vasculitis Study Group Database. Arthritis Rheum. 2010;62:616-626.
- Rothschild PR, Pagnoux C, Seror R, et al. Ophthalmologic manifestations of systemic necrotizing vasculitides at diagnosis: a retrospective study of 1286 patients and review of the literature. Semin Arthritis Rheum. 2013;42:507-514.
Test yourself
A few questions straight from this article.
-
How does the Chapel Hill consensus define polyarteritis nodosa?
Chapel Hill defines polyarteritis nodosa as necrotizing arteritis of medium or small arteries without glomerulonephritis, and it is not linked to ANCA. -
Which infection is a classic trigger of polyarteritis nodosa?
Many cases are idiopathic, but hepatitis B infection is a classic trigger, so every patient should be tested for it. -
Which monogenic disorder mimics polyarteritis nodosa in children?
Deficiency of adenosine deaminase 2 (ADA2 mutations) mimics the disease in children, with strokes, fever and skin changes, and anti-TNF therapy helps. -
How do choroidal infarcts of polyarteritis nodosa appear on fluorescein angiography?
Occluded choroidal arteries cause patchy infarcts; fluorescein shows delayed filling with early hypofluorescence and late staining. -
Which complication can follow choroidal infarcts in polyarteritis nodosa?
Serous detachment of the retina can follow choroidal infarction, so patients may notice central blur. -
Why should blood pressure be checked at every visit in polyarteritis nodosa?
Renal involvement can cause severe hypertension with exudates and disc swelling, yet not every finding should be attributed to hypertension. -
Which mimic of polyarteritis nodosa causes ischemic optic neuropathy and choroidal ischemia in older patients?
Giant cell arteritis causes ischemic optic neuropathy and choroidal ischemia in older patients, whereas granulomatosis with polyangiitis shows scleritis and orbital disease. -
Which visceral angiography finding is typical of polyarteritis nodosa?
Biopsy of affected tissue or visceral angiography confirms the diagnosis, and aneurysms in renal or mesenteric arteries are typical. -
What is the first step in treating polyarteritis nodosa?
High-dose steroids come first, cyclophosphamide is added for severe disease, and hepatitis B-related disease is treated with antivirals and plasma exchange. -
What does eye involvement indicate about polyarteritis nodosa?
Eye involvement signals severe disease; early treatment improves survival and organ outcomes, while vision loss after infarcts can be permanent.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.