
A posterior staphyloma is an outward bulging or ectasia of the sclera, choroid, and retinal pigment epithelium at the back of a highly myopic eye, and understanding what it is, rather than jumping straight to how it is treated, is the starting point for understanding one of the most important structural drivers of vision loss in pathologic myopia.
Why the Back of a Myopic Eye Bulges Outward
In high myopia, progressive axial elongation of the eye is accompanied by thinning and weakening of the sclera, particularly around the posterior pole, and in a subset of highly myopic eyes this weakened scleral shell can no longer maintain its normal, smoothly curved shape under normal intraocular pressure.
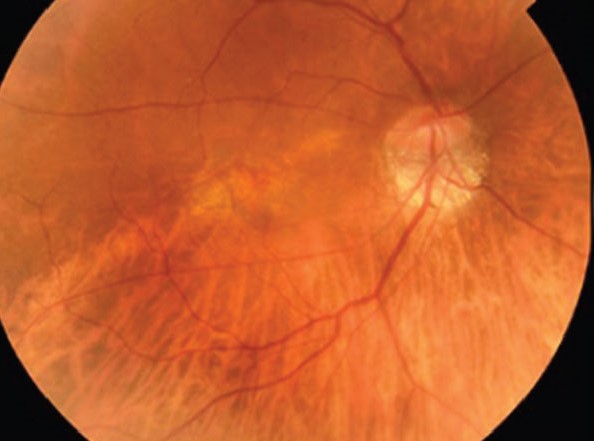
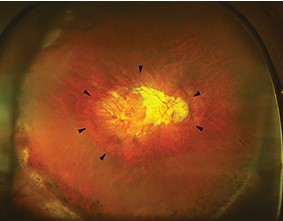
The result is a posterior staphyloma: a localized area where the sclera, along with the choroid and retinal pigment epithelium draped over it, bulges outward beyond the normal contour of the globe, creating a distinct change in curvature that can be seen on imaging and, in more advanced cases, even suspected on careful fundus examination.
Who Develops a Posterior Staphyloma
- High myopia is the dominant risk factor, with risk increasing substantially as axial length and refractive error increase
- Longer axial length and older age are both associated with a higher prevalence of staphyloma among myopic eyes
- Not every highly myopic eye develops a staphyloma, and the reasons some eyes develop this scleral weakness while others with similar refractive error do not are not fully understood, though genetic and biomechanical factors are thought to play a role
Fundus Explorer Pro
Photograph the retinal findings described here with the phone already in your pocket — 22 D optics and built-in illumination in one handheld unit.
From Choroida — the team behind this siteClassification
Posterior staphylomas are classified by their location and shape, most commonly using a system originally described by Curtin, which divides staphylomas into several types based on whether the bulge is centered on the posterior pole, the optic disc, or is more diffusely distributed, and whether it is a single, well-defined bulge or a more complex, compound shape.
This classification matters clinically because the location and extent of the staphyloma correlates with which structures, the macula, the optic nerve, or both, are most directly affected, and with the pattern of visual field or acuity loss a given patient is likely to experience.
Why a Staphyloma Threatens Vision
The outward bulge is not simply a structural curiosity, since the stretching and thinning of the choroid and retinal pigment epithelium draped over it predisposes the overlying retina to a cascade of secondary problems.
- Progressive chorioretinal atrophy, as the stretched tissue thins further over time
- Lacquer cracks, breaks in Bruch membrane that can develop within the staphyloma and serve as an entry point for choroidal neovascularization
- Myopic choroidal neovascularization, a serious complication that can cause acute, significant central vision loss if it develops within or near the macula
- Myopic traction maculopathy, including foveoschisis and, in advanced cases, macular detachment, related to the mechanical stress the abnormal curvature places on the overlying retina
- Optic nerve and peripapillary changes when the staphyloma involves the region around the disc, which can complicate both vision and the assessment of coexisting glaucoma in these eyes
Clinical Recognition
- Fundus examination in an eye with high myopia and significant chorioretinal atrophy or a visibly altered posterior contour should prompt consideration of an underlying staphyloma
- B-scan ultrasound can demonstrate the characteristic outward bulge and has traditionally been a key tool for confirming and characterizing staphyloma shape
- Optical coherence tomography, particularly wide-field and swept-source technology capable of imaging the peripheral posterior pole, increasingly allows direct, detailed visualization of staphyloma extent and its relationship to the macula and optic nerve
- Wide-field fundus photography helps document the extent of associated chorioretinal atrophy and supports monitoring for change over time
Monitoring
Patients with high myopia and a known or suspected posterior staphyloma benefit from regular dilated fundus examination, given their elevated risk for the progressive complications above, with particular attention to any new distortion or vision change that could signal choroidal neovascularization or traction maculopathy developing.
Home monitoring with an Amsler grid can help patients detect early symptoms of macular involvement between formal examinations, supporting earlier detection of a new complication.
Management
There is no treatment that reverses an established posterior staphyloma itself, so management is centered on monitoring for and treating its complications as they arise.
- Myopic choroidal neovascularization is treated with anti-VEGF therapy, following similar principles to neovascular age-related macular degeneration, though with its own specific considerations given the different underlying eye
- Myopic traction maculopathy and foveoschisis, when visually significant, may be managed surgically, and in eyes with a large, progressive staphyloma contributing to macular traction or detachment, macular buckle surgery is a specific surgical option that directly addresses the underlying staphyloma by indenting the sclera at the site of the bulge, used when vitrectomy alone is insufficient (see macular buckle surgery for myopic staphyloma for a detailed look at this specific procedure)
- Correction of refractive error and general low vision support, given that many patients with an advanced staphyloma have significant baseline visual impairment independent of any single treatable complication
Prognosis
The presence of a posterior staphyloma is itself a marker of more advanced pathologic myopia and carries a higher lifetime risk of the vision-threatening complications described above compared with high myopia without staphyloma.
With regular monitoring, prompt treatment of choroidal neovascularization when it develops, and, in appropriate candidates, surgical management of significant traction maculopathy, many patients maintain functional vision for years, even as the underlying staphyloma itself remains a permanent structural feature of the eye.
Related Reading


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Curtin BJ. The posterior staphyloma of pathologic myopia. Trans Am Ophthalmol Soc. 1977;75:67-86.
- Ohno-Matsui K, Kawasaki R, Jonas JB, et al. International photographic classification and grading system for myopic maculopathy. Am J Ophthalmol. 2015;159:877-883.
- Moriyama M, Ohno-Matsui K, Hayashi K, et al. Topographic analyses of shape of eyes with pathologic myopia by high-resolution three-dimensional magnetic resonance imaging. Ophthalmology. 2011;118:1626-1637.
- Ohno-Matsui K, Lai TY, Lai CC, Cheung CM. Updates of pathologic myopia. Prog Retin Eye Res. 2016;52:156-187.
Test yourself
A few questions straight from this article.
-
A posterior staphyloma consists of an outward bulge of which structures?
The staphyloma is an ectasia in which the sclera, with the choroid and retinal pigment epithelium draped over it, bulges beyond the normal contour of the globe at the posterior pole. -
What mechanism allows a posterior staphyloma to form in a highly myopic eye?
Progressive axial elongation thins and weakens the sclera around the posterior pole until the shell can no longer hold its smoothly curved shape at normal intraocular pressure. -
Which factors are associated with a higher prevalence of staphyloma among myopic eyes?
Risk rises substantially with axial length and refractive error, and both longer axial length and older age carry a higher prevalence, although not every highly myopic eye develops one. -
The Curtin system classifies posterior staphylomas according to which features?
Curtin's system divides staphylomas by location and shape: centred on the posterior pole, on the optic disc, or more diffuse, and single and well defined versus compound. -
What is the central principle of managing an established posterior staphyloma?
No treatment reverses an established posterior staphyloma, so care centres on surveillance and on treating the complications as they arise. -
What are lacquer cracks in an eye with a posterior staphyloma?
Lacquer cracks are breaks in Bruch membrane that can develop within a staphyloma and act as an entry point for choroidal neovascularization. -
Myopic traction maculopathy within a staphyloma includes which findings?
Mechanical stress from the abnormal curvature produces myopic traction maculopathy, which spans foveoschisis through to macular detachment in advanced cases. -
Which investigation has traditionally been key to confirming and characterizing staphyloma shape?
B-scan ultrasound demonstrates the characteristic outward bulge and has long been the key tool for confirming and characterizing staphyloma shape. -
How is myopic choroidal neovascularization complicating a staphyloma treated?
Myopic choroidal neovascularization is treated with anti-VEGF therapy, following principles similar to neovascular age-related macular degeneration but with considerations specific to the myopic eye. -
What does macular buckle surgery do in an eye with a large, progressive staphyloma?
Macular buckle surgery addresses the staphyloma directly by indenting the sclera at the bulge, and is used for macular traction or detachment when vitrectomy alone is insufficient.
