Ocular mucous membrane pemphigoid demands a genuinely different mindset from most external eye disease, since this is a condition where the visible inflammation at any given visit can look deceptively mild, while irreversible scarring continues to accumulate quietly underneath, which is exactly why the standard of care has shifted firmly toward early, proactive systemic immunosuppression rather than waiting to treat until inflammation looks severe.
An Autoimmune Attack on the Conjunctival Basement Membrane
Mucous membrane pemphigoid is an autoimmune condition in which autoantibodies target proteins within the basement membrane zone of mucous membranes, including the conjunctiva, and this immune-mediated attack produces chronic, progressive subepithelial fibrosis and scarring, distinct from the more acute, inflammation-dominant presentation of some other causes of conjunctivitis.
Why Progression Can Be Deceptively Quiet
A defining, frustrating feature of this condition is that the degree of visible conjunctival inflammation at any given examination does not reliably correlate with the underlying rate of scarring progression, meaning a conjunctiva that looks only mildly inflamed can still be accumulating significant, permanent scar tissue, and this disconnect between apparent disease activity and actual progression is precisely why clinical staging based on cumulative scarring, rather than inflammation alone, guides treatment decisions in this condition.
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteClinical Staging
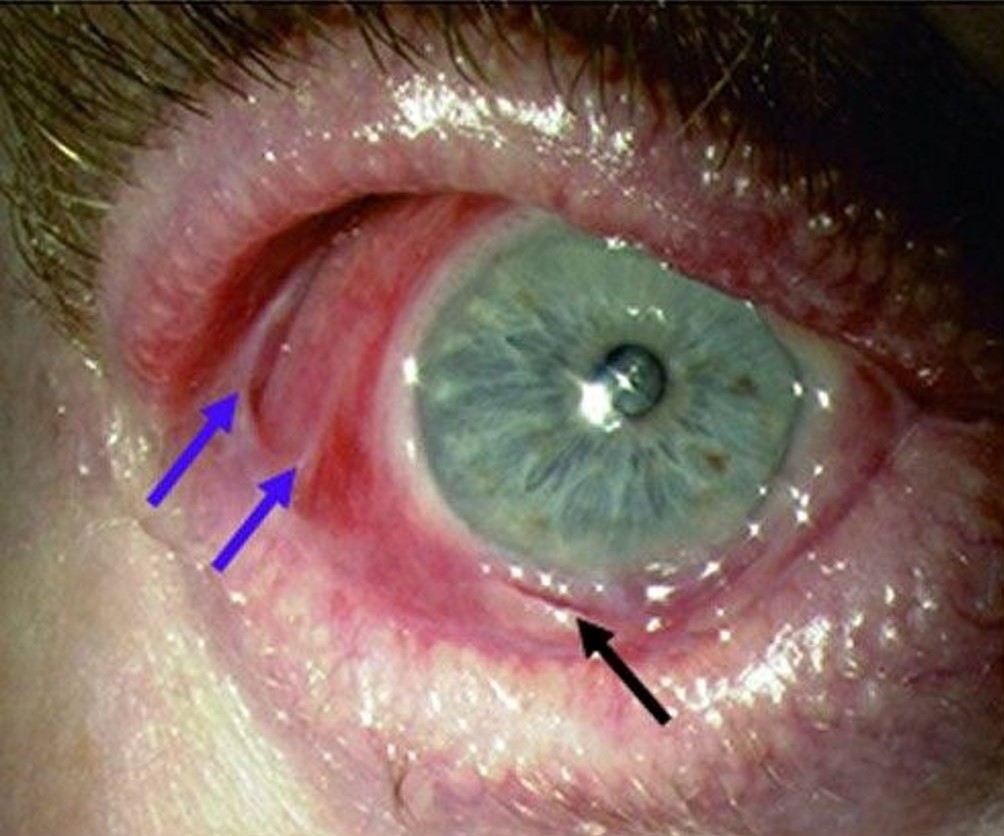
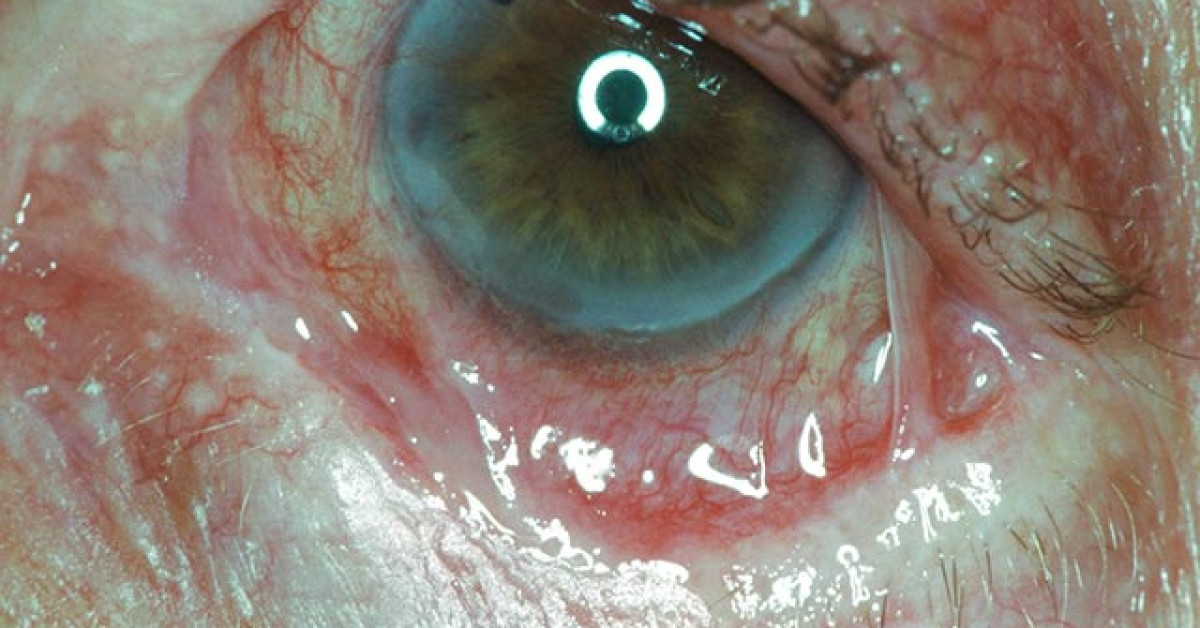
Ocular mucous membrane pemphigoid is staged based on the degree of cumulative conjunctival scarring, commonly using a system assessing fornix foreshortening and symblepharon formation, progressing from early, subtle subconjunctival fibrosis through progressive fornix shortening to, in the most advanced stage, complete obliteration of the fornices with severe symblepharon and ankyloblepharon.
This staging supports objective tracking of disease progression over time, which is particularly important given the disconnect between visible inflammation and actual cumulative scarring described above.
Clinical Features
- Chronic conjunctivitis with progressive subconjunctival fibrosis, best appreciated on careful examination of the fornices and by comparing serial examinations over time for interval progression
- Symblepharon formation, adhesions between the palpebral and bulbar conjunctiva, progressively restricting eye movement and eyelid function as the disease advances
- Progressive dry eye, related to destruction of conjunctival goblet cells and, in more advanced disease, meibomian gland and lacrimal duct involvement
- Trichiasis and entropion from eyelid margin scarring, contributing further mechanical trauma to an already compromised ocular surface
- In advanced disease, severe corneal scarring, vascularization, and keratinization can develop, related to the cumulative effects of chronic surface inflammation, scarring, and mechanical trauma
- Other mucous membranes, including the oral mucosa, are frequently also affected, and examination and history for oral, nasal, or other mucosal involvement is an important part of complete evaluation
Diagnostic Evaluation
- Conjunctival biopsy with direct immunofluorescence, demonstrating characteristic autoantibody and complement deposition along the basement membrane zone, supports definitive diagnosis, though biopsy from an actively inflamed area away from already heavily scarred tissue improves diagnostic yield
- Clinical staging of fornix depth and symblepharon extent, with serial documentation supporting objective tracking of progression over time
- Examination for other mucosal involvement, including oral, nasal, and, less commonly, esophageal or laryngeal disease, given the broader mucous membrane involvement this condition can produce
Management
Early Systemic Immunosuppression
Given the recognized disconnect between visible inflammation and actual scarring progression, current management strongly favors early initiation of systemic immunosuppressive therapy once the diagnosis is confirmed, rather than reserving systemic treatment only for visually dramatic or clearly active-appearing disease, since waiting for more obvious inflammation risks allowing substantial, irreversible scarring to accumulate in the interim.
- Treatment typically follows an escalating approach based on disease severity, from dapsone for milder disease to more potent systemic immunosuppressive agents, and in some cases biologic therapy, for more severe or rapidly progressive disease
- Treatment is generally coordinated with dermatology or rheumatology, given the systemic nature of the underlying autoimmune process and the specialized experience these specialties bring to systemic immunosuppressive management
Managing the Ocular Surface
Aggressive lubrication, management of any associated trichiasis or entropion, and treatment of secondary complications, including infection or corneal compromise, are important supportive components alongside the essential systemic disease-modifying treatment.
Surgical Considerations
Surgery on an actively inflamed eye with mucous membrane pemphigoid carries a recognized risk of inducing further scarring as a response to the surgical trauma itself, so elective surgical procedures, including cataract surgery or eyelid procedures, are generally deferred until disease activity is well controlled with systemic treatment whenever this is clinically feasible.
Prognosis
With early recognition and prompt initiation of appropriate systemic immunosuppressive treatment, disease progression can often be significantly slowed or halted, preserving ocular surface function and reducing the risk of the severe, vision-threatening complications advanced disease can produce.
Delayed diagnosis or undertreatment, allowing the disconnect between mild-appearing inflammation and ongoing scarring to go unaddressed, is the central driver of poor long-term outcomes in this condition, reinforcing why early, proactive systemic treatment, rather than a wait-and-watch approach based on visible inflammation alone, has become the standard of care.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Foster CS. Cicatricial pemphigoid. Trans Am Ophthalmol Soc. 1986;84:527-663.
- Mondino BJ. Cicatricial pemphigoid and erythema multiforme. Ophthalmology. 1990;97:939-952.
- Chan LS, Ahmed AR, Anhalt GJ, et al. The first international consensus on mucous membrane pemphigoid. Arch Dermatol. 2002;138:370-379.
- Saw VP, Dart JK. Ocular mucous membrane pemphigoid: diagnosis and management strategies. Ocul Surf. 2008;6:128-142.
Test yourself
A few questions straight from this article.
-
In mucous membrane pemphigoid, autoantibodies are directed against which target?
Autoantibodies target proteins in the basement membrane zone of mucous membranes including the conjunctiva, driving chronic progressive subepithelial fibrosis. -
What makes progression in ocular mucous membrane pemphigoid deceptively quiet?
A conjunctiva that looks only mildly inflamed can still be laying down significant permanent scar tissue, so apparent activity and true progression are disconnected. -
When should systemic immunosuppressive therapy be started in ocular mucous membrane pemphigoid?
Because waiting for visibly severe inflammation allows irreversible scarring to accumulate, current management strongly favours starting systemic immunosuppression as soon as the diagnosis is confirmed. -
Clinical staging of ocular mucous membrane pemphigoid is based on which assessment?
Staging rests on cumulative conjunctival scarring, commonly assessed through fornix foreshortening and symblepharon formation rather than on inflammation alone. -
What characterises the most advanced stage of ocular mucous membrane pemphigoid?
The staging sequence runs from subtle subconjunctival fibrosis through progressive fornix shortening to complete fornix obliteration with severe symblepharon and ankyloblepharon. -
Which systemic agent is typically used for milder ocular mucous membrane pemphigoid before escalation?
Treatment escalates with severity, beginning with dapsone in milder disease and moving to more potent immunosuppressive agents or biologic therapy in severe or rapidly progressive cases. -
Progressive dry eye in ocular mucous membrane pemphigoid is driven by destruction of which structures?
Goblet cell destruction drives the dryness, and in more advanced disease meibomian gland and lacrimal duct involvement compound it. -
Which investigation supports definitive diagnosis of ocular mucous membrane pemphigoid?
Direct immunofluorescence on conjunctival biopsy demonstrates characteristic autoantibody and complement deposition along the basement membrane zone. -
Which site gives the best diagnostic yield when biopsying the conjunctiva in mucous membrane pemphigoid?
Taking the specimen from actively inflamed conjunctiva rather than from already heavily scarred tissue improves diagnostic yield. -
Why is elective surgery deferred until disease activity is controlled in ocular mucous membrane pemphigoid?
Surgery on an actively inflamed eye risks provoking further scarring in response to the surgical trauma, so cataract and eyelid procedures are deferred until control is achieved.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.