Skew deviation is a vertical misalignment of the eyes caused by disruption of otolith-related brainstem or cerebellar pathways, distinct from the more familiar vertical strabismus caused by an extraocular muscle or cranial nerve palsy.
Because it can look clinically similar to a fourth nerve palsy on a routine cover test, correctly identifying skew deviation matters directly for localization and for recognizing when a central, sometimes acute, neurological process is the actual underlying cause.
The distinction is not academic: a fourth nerve palsy is usually benign or vasculopathic, while skew deviation can be the presenting sign of a brainstem stroke.
Skew deviation is far less common in everyday practice than fourth nerve palsy, which is part of why it is so often overlooked as a possibility when a patient presents with a seemingly straightforward vertical diplopia.
Mechanism
Skew deviation arises from an imbalance in the otolith-ocular reflex pathways, which normally use vestibular input about head tilt to help coordinate torsional and vertical eye position.
Lesions anywhere along the brainstem and cerebellar pathways carrying this vestibular information, most often in the pons or medulla, can disrupt the normal balance between the two sides, producing a vertical misalignment that does not follow the pattern expected from an isolated extraocular muscle or cranial nerve problem.
Skew deviation is frequently one component of the ocular tilt reaction, a triad that also includes head tilt and ocular torsion, reflecting the same underlying otolith pathway disruption acting on multiple aspects of eye and head position simultaneously.
Clinical Presentation
- Vertical diplopia, the presenting symptom in most cases, sometimes accompanied by a sense of tilted or rotated vision from associated torsion
- A compensatory head tilt, often toward the side of the hypotropic (lower) eye, part of the broader ocular tilt reaction
- Associated brainstem signs, including dysarthria, ataxia, facial weakness, or sensory changes, depending on the location and extent of the underlying lesion
- A vertical deviation that, unlike a typical fourth nerve palsy, does not reliably increase in a specific single gaze position or with head tilt to one particular side in the pattern classically taught for muscle palsies
All-fit Slit-Lamp Adapter
Record and share exactly what you see at the slit lamp. One adapter fits any slit lamp or surgical microscope — and any smartphone.
From Choroida — the team behind this siteDistinguishing Skew Deviation From Fourth Nerve Palsy
Both conditions can produce a vertical misalignment with head tilt, which is exactly why skew deviation is so often initially mistaken for a fourth nerve palsy on cursory exam.
The three-step test, classically used to localize a vertical strabismus to a specific muscle, can be misleading in skew deviation, since the deviation does not necessarily follow the predictable pattern expected from an isolated trochlear nerve or superior oblique problem.
Associated neurological signs, an acute or subacute onset without a clear vasculopathic risk profile, and a variable or comitant deviation pattern across different gaze positions should raise suspicion for skew deviation and prompt neuroimaging rather than assuming a benign fourth nerve palsy.
Causes
Brainstem stroke is the most important and time-sensitive cause to consider, particularly in a patient with vascular risk factors and any associated neurological symptoms suggesting posterior circulation involvement.
Multiple sclerosis and other demyelinating disease, brainstem or cerebellar tumors, and, less commonly, severe peripheral vestibular disease can also produce skew deviation through disruption of the same otolith pathways.
The acuity and context of presentation matter considerably for prioritizing the differential: a sudden onset in an older patient with vascular risk factors points strongly toward stroke, while a more gradual course in a younger patient might prompt broader consideration of demyelinating or structural causes.
Evaluation and Management
Urgent neuroimaging, typically MRI given its superior sensitivity for brainstem pathology compared to CT, is warranted in any patient with new skew deviation, especially when the onset is acute or there are other neurological findings suggesting a stroke.
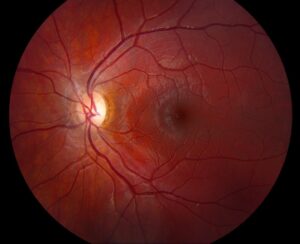
Fundus examination for excyclotorsion or incyclotorsion, part of assessing the full ocular tilt reaction, adds supportive evidence for the diagnosis and can help track the deviation over time.
Treatment is directed entirely at the underlying cause, whether that means acute stroke management, treatment of demyelinating disease, or addressing a structural lesion, since there is no treatment for skew deviation itself independent of its cause.
Prism correction or, for persistent, stable deviations once the acute underlying process has been addressed, strabismus surgery can help manage residual diplopia that does not resolve on its own.
Coordination with neurology is essential throughout, both for the acute workup and for longer-term management, since the ophthalmologist’s role here is largely about recognizing the sign and triggering the right referral rather than managing the underlying neurological disease directly.


Document what you see
Two smartphone imaging tools built for everyday clinic use — one for the slit lamp, one for the fundus.
From Choroida — the team behind this siteReferences
- Brandt T, Dieterich M. Skew deviation with ocular torsion: a vestibular brainstem sign of topographic diagnostic value. Annals of Neurology.
- American Academy of Ophthalmology. Basic and Clinical Science Course, Section 5: Neuro-Ophthalmology.
- Wong AM. Understanding skew deviation and a new clinical test to differentiate it from trochlear nerve palsy. Journal of AAPOS.
Test yourself
A few questions straight from this article.
-
Disruption of which pathways produces skew deviation?
Skew deviation comes from imbalance in the otolith-ocular reflex pathways running through the brainstem and cerebellum, not from a muscle or cranial nerve lesion. -
Why does distinguishing skew deviation from a fourth nerve palsy matter clinically?
A fourth nerve palsy is usually benign or vasculopathic, whereas skew deviation can be the presenting sign of a brainstem stroke, so the distinction drives localisation and urgency. -
Skew deviation is frequently one component of which clinical triad?
The ocular tilt reaction combines skew deviation, head tilt and ocular torsion, all reflecting the same otolith pathway disruption. -
In skew deviation, the compensatory head tilt is usually toward which side?
The head tilt is often toward the side of the lower, hypotropic eye and forms part of the broader ocular tilt reaction. -
Lesions causing skew deviation most often sit in which structures?
Lesions anywhere along the vestibular pathways can cause skew deviation, but the pons and medulla are the commonest sites. -
What is the limitation of the three-step test when skew deviation is present?
The three-step test can be misleading in skew deviation, because the vertical deviation does not necessarily follow the pattern predicted for an isolated superior oblique problem. -
Which cause of skew deviation is the most time-sensitive to identify?
Brainstem stroke is the most important and time-sensitive cause, particularly in a patient with vascular risk factors and other posterior circulation symptoms. -
Which imaging study is preferred for a patient with new skew deviation?
Urgent MRI is warranted because it is considerably more sensitive than CT for brainstem pathology. -
What principle guides treatment of skew deviation?
There is no treatment for skew deviation itself independent of its cause, so management targets the stroke, demyelinating disease or structural lesion responsible. -
How is residual diplopia managed once the underlying cause of skew deviation is treated?
Prisms help residual diplopia, and strabismus surgery is an option for a persistent, stable deviation once the acute underlying process has been addressed.

Writes and reviews the clinical articles on Educate. Every post is checked against peer-reviewed sources before it goes live.